
Rarely tested
Most physicians who diagnose Lyme disease do not order co-infection testing. The work-up stops at Borrelia, and the second and third organisms from the same bite stay invisible.
Rosenheimer Str. 6-8, 83043 Bad Aibling, Germany · info@clinicum-stgeorg.de
Tick-Borne Co-Infections
Ticks carry far more than Borrelia. Many patients with chronic Lyme disease carry one or more co-infections that complicate diagnosis, alter symptoms, and require targeted treatment beyond standard Lyme protocols.
Night sweats nobody asked about. Pain in the soles of your feet in the morning. Anxiety that arrived out of nowhere, in a life that was not anxious before. You were treated for one organism. The tick did not carry only one.
When co-infections are present alongside Borrelia, the clinical picture becomes more complex and severe. Patients with co-infections typically experience more intense symptoms, slower response to treatment, and greater diagnostic confusion.
Signs that co-infections may be present include:

Babesia is looked for in the blood smear and by PCR, with serology as a second line; Bartonella by serology and PCR. Both can be negative in a long-standing infection, so the result is read with the symptom pattern. A standard Lyme work-up usually does not include them, although ticks frequently carry several pathogens at once (Sanchez-Vicente et al., 2019) and Babesia co-infection has been measured in tick-borne disease patients (Nijjar et al., 2024). The co-infection panel is part of every Lyme work-up at the hospital.
Most physicians who diagnose Lyme disease do not order co-infection testing. The work-up stops at Borrelia, and the second and third organisms from the same bite stay invisible.
Antibody tests for co-infections share the limits of the Lyme antibody test: they can miss infections in patients with a suppressed immune response, and several of the organisms are hard to culture or to find by PCR in a routine blood sample.
Co-infection symptoms overlap with Lyme symptoms and with each other. Night sweats, air hunger and burning soles are the clues that point past Borrelia; without them being asked about, the plan stays incomplete.
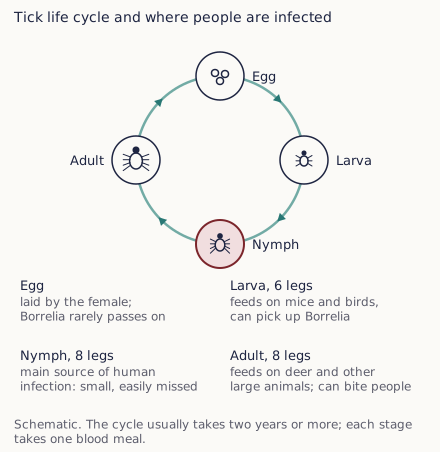
Bartonella species (particularly B. henselae and B. quintana) are intracellular bacteria. The established routes to humans are cat scratches and bites and cat fleas for B. henselae, and body lice for B. quintana. Bartonella DNA has been found in ticks, but transmission by a tick bite to humans is debated and has not been established (Telford and Wormser, 2010). Because it can cause a similar multi-system picture, Bartonella is part of the co-infection panel for patients whose symptoms persist after Lyme disease.
Bartonella has a particular affinity for endothelial cells (blood vessel lining) and red blood cells, which explains its wide-ranging vascular and neurological symptoms. It can cause vasculitis, neuroinflammation, and psychiatric manifestations that are frequently misdiagnosed as primary mental health conditions.
Bartonella requires specific antibiotic combinations, typically including agents that achieve high intracellular concentrations such as azithromycin, rifampin, or fluoroquinolones. Treatment duration is often longer than for Borrelia alone, and response monitoring is essential.
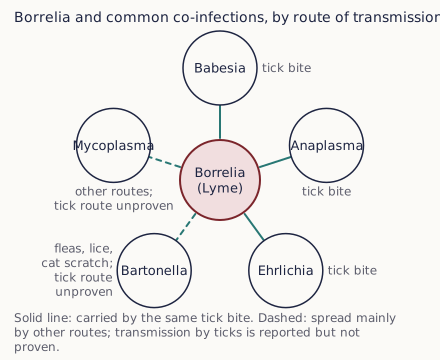
Babesia species (B. microti, B. duncani and others) are protozoan parasites that infect red blood cells, like the malaria parasite. Babesia is transmitted by the same Ixodes ticks that carry Borrelia and is found together with it. Because it is a parasite, it does not respond to the antibiotics used for Lyme disease; the babesiosis guideline recommends antiparasitic combinations (Krause et al., 2021).
Babesiosis causes hemolysis as parasites rupture red blood cells, which explains the air hunger, drenching sweats and profound fatigue. It can be severe in immunocompromised patients and is harder to clear when Borrelia is present at the same time.
Babesia is treated with antiparasitic agents, typically atovaquone with azithromycin or clindamycin with quinine. Treatment continues until the parasitemia clears and the symptoms settle, which often takes longer than the Borrelia course.
Ehrlichia and Anaplasma are obligate intracellular bacteria that infect white blood cells. Ehrlichia chaffeensis infects monocytes (human monocytic ehrlichiosis), while Anaplasma phagocytophilum infects granulocytes (human granulocytic anaplasmosis). Both are transmitted by ticks and can cause acute and chronic illness.
These infections directly compromise immune function by infecting the very cells responsible for fighting infection. This immune suppression can make concurrent Borrelia infection more difficult to clear and can mask the typical immune responses used for serological diagnosis.
Doxycycline is the first-line treatment for both Ehrlichia and Anaplasma. In chronic co-infection, longer treatment courses are often necessary, and monitoring of white blood cell counts and liver function guides treatment duration.

Beyond the major tick-borne co-infections, chronic Lyme patients frequently harbor additional opportunistic infections that contribute to their symptom burden and complicate recovery:
The co-infection panel tests for all of the above pathogens with a combination of serological, molecular and cellular immune tests in the hospital laboratory. Physicians who treat tick-borne illness every day read the results and write the plan for every identified infection.
At St. George Hospital, co-infection treatment is not an afterthought. It is an integral part of every Lyme disease treatment plan. Our approach recognizes that treating Borrelia alone while co-infections persist will never achieve lasting improvement.
The primary treatment for co-infections is Intravenous Low-Level Laser Therapy (LLLT), delivered as 10 sessions in the dedicated Co-Infection Module. A fiber-optic catheter is inserted into a peripheral vein, delivering laser light directly into the bloodstream. The therapy stimulates mitochondrial function and ATP synthesis at the cellular level. Six wavelengths target different therapeutic effects: blue (405 nm) with Riboflavin for antimicrobial action against Bartonella, Babesia, and intracellular pathogens; green (532 nm) for improved oxygen uptake via hemoglobin binding; yellow (589 nm) for detoxification and serotonin metabolism support; red (635 nm) for deep tissue anti-inflammatory effect and microcirculation improvement; infrared (810 nm) for deepest tissue penetration (5–7 cm) and stem cell activation; and UV light for immune activation and direct pathogen inactivation. This is combined with apheresis blood purification, and in severe cases, Plasma Exchange or Red Blood Cell Exchange.
Our complete co-infection treatment strategy includes:
For patients from abroad, the co-infection module is scheduled as part of inpatient Lyme disease treatment in Germany: a video consultation in English before you travel, the work-up in the first days, and the antimicrobial plan for each pathogen written from it.
The evidence is graded by claim. That ticks and tick-borne disease are polymicrobial, so that a Borrelia-only work-up can miss a second organism, is strong (Sanchez-Vicente et al., 2019; Nijjar et al., 2024). The treatment of babesiosis with antiparasitic combinations rests on a guideline (Krause et al., 2021), and doxycycline for Ehrlichia and Anaplasma is standard care. The evidence for intravenous laser therapy and apheresis in co-infections is limited.
In our clinical experience since 1995, an untreated co-infection is the most frequent finding in patients whose symptoms continued after a Lyme-only course. That is an observation from the ward, not a trial result, and it is why the co-infection panel is part of every Lyme work-up here.
Blood filtration removes inflammatory complexes and pathogen-associated toxins that drive co-infection symptoms.
What H.E.L.P. apheresis involves →Medical ozone has direct antimicrobial properties against co-infection organisms and enhances immune function.
What ozone therapy involves →Two sessions in the core Lyme module; the heat is aimed at Borrelia, and the co-infection module follows.
What a whole-body hyperthermia session involves →Thymus peptides and micronutrient infusions to support the immune response against persistent intracellular organisms.
What immune therapy involves →Intravenous laser light with riboflavin, ten sessions in the co-infection module.
What photodynamic therapy involves →No. Babesia is a parasite of red blood cells, related to the malaria parasite, and Lyme disease is caused by the bacterium Borrelia. The same Ixodes tick can transmit both, which is why they are often found together. Babesia does not respond to the antibiotics used for Borrelia and needs antiparasitic treatment of its own.
Babesia is looked for in the blood smear and by PCR, with serology as a second line. Bartonella is tested by serology and PCR; both can be negative in a long-standing infection, so the result is read with the symptom pattern. Both tests are part of the co-infection panel in the hospital laboratory.
No. Doxycycline is the first-line agent for Ehrlichia and Anaplasma and is used in Lyme disease, but Babesia is a parasite and is treated with antiparasitic combinations such as atovaquone with azithromycin, following the babesiosis guideline. A patient treated only with doxycycline keeps the Babesia.
Yes. In the program the core Lyme module comes first and the co-infection module follows, with antimicrobial agents chosen for each confirmed pathogen, intravenous laser therapy and apheresis. Whole-body hyperthermia belongs to the Lyme module and is not repeated for the co-infections.
Bartonella, Babesia, Ehrlichia, Anaplasma, Rickettsia, Chlamydia pneumoniae, Mycoplasma pneumoniae and Yersinia. The panel combines serological, molecular and cellular immune tests and is part of every Lyme work-up at the hospital.
The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.
Munich Airport (MUC), about 60 minutes by car.