
ME/CFS
Chronic fatigue and ME/CFS treatment
ME/CFS is a measurable illness. St. George Hospital in Bad Aibling, Germany, runs a two- to three-week inpatient program for ME/CFS and post-viral fatigue: a work-up first, then a plan written from your findings and carried out on our ward.
Chronic fatigue
About the condition and its treatment
- About the conditionUnderstanding CFS
ME/CFS is a multi-system disease defined by profound fatigue, post-exertional malaise, unrefreshing sleep and cognitive or orthostatic symptoms that persist for months.
- About the conditionDiagnosis
ME/CFS diagnosis criteria name the symptoms; the standard blood panel does not measure the systems behind them.
- About the conditionTreatment
ME/CFS treatment at St. George Hospital is an inpatient program of two to three weeks written from your findings: blood purification where autoantibodies or …
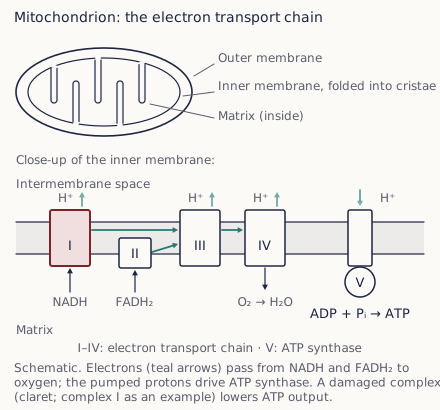
- About the conditionMitochondrial dysfunction
Mitochondria are the power plants of every cell.
- Treatment program for international patientsLong COVID and ME/CFS program
Many patients with Long COVID or ME/CFS have normal results in standard tests and still cannot manage daily life.
- TherapyImmunoadsorption
Immunoadsorption is an apheresis procedure that removes antibodies from the plasma.
- TherapyIHHT
IHHT is a breathing therapy. Through a mask you inhale air with less oxygen than usual for a few minutes, then air with more, in cycles of 30 to 40 minutes.
- TherapyNAD+ IV
A slow intravenous infusion of nicotinamide adenine dinucleotide (NAD+), the coenzyme every cell uses to make energy and repair DNA, given on our ward over 2–4 …
What is ME/CFS?
Myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) is a multisystem illness defined by one feature above all: physical or mental exertion makes every symptom worse, often 24 to 72 hours later. The 2015 Institute of Medicine report set these criteria and called it a physical disease (Clayton, JAMA, 2015).
A standard blood panel does not measure natural killer cell function, autoantibodies against receptors of the autonomic nervous system, or how cells make energy under load. Research groups have measured all three in patient cohorts (the biology of ME/CFS in plain language). Since 2020, many new patients have ME/CFS that began with COVID-19; the Long COVID program uses the same work-up and most of the same therapies. Protocols are written by Dr. Julian Douwes, Chief Medical Officer, and supervised on the ward by Dr. Martin Rößner, Chief Physician.
What are the symptoms of ME/CFS?
Post-exertional malaise separates ME/CFS from ordinary exhaustion, and it is measurable: in controlled studies, the symptoms that follow exertion distinguish patients from healthy controls (Mateo et al., 2020).
- Post-exertional malaise
All symptoms worsen after physical or mental effort, often 24 to 72 hours later, for days or weeks.
- Unrefreshing sleep
Patients sleep enough hours and still wake as tired as they went to bed.
- Cognitive impairment
Slow thinking, word-finding problems and poor short-term memory (brain fog).
- Orthostatic intolerance
Dizziness or a racing heart on standing. Many patients meet criteria for POTS, which we test for on the ward.
- Immune symptoms
Recurring sore throats, tender lymph nodes and infections that take weeks to clear.
- Pain
Muscle and joint pain, headaches, and sensitivity to light, sound, touch and temperature.
Seek an assessment if exertion has reliably worsened your symptoms for six months or more, if standing up has become a symptom in itself, or if exercising through it made you worse.
How do we diagnose ME/CFS?
How do we diagnose ME/CFS?
We apply the published criteria first, the Institute of Medicine criteria of 2015 and the International Consensus Criteria of 2011 (Carruthers et al., 2011), then measure the systems behind the symptoms: immune function and receptor autoantibodies, mitochondrial markers, orthostatic heart-rate response, reactivated infections, hormones and gut markers. The baseline from the first two days is measured again in week two. How we diagnose ME/CFS

How do we treat ME/CFS at St. George Hospital?
No single drug treats ME/CFS, because the illness has no single cause. Your plan combines therapies according to the work-up, spaced so that the program itself does not trigger post-exertional malaise. Immunoadsorption, H.E.L.P. apheresis, IHHT and the infusion protocols are outside standard care for ME/CFS: treatment attempts your physician decides with you.
How the ME/CFS program runs
Two to three weeks as an inpatient, longer for severe ME/CFS when the physician recommends it. Every step is paced.
Work-up
The functional medicine work-up, read by your attending physician. The baseline is repeated in week two.
Blood purification
Immunoadsorption for receptor autoantibodies; H.E.L.P. apheresis when the findings point to microclots and impaired microcirculation.
Energy metabolism
IHHT and NAD+ infusions; hyperbaric oxygen for pronounced brain fog.
Immune system
Immune therapy with thymus peptides; mild whole-body hyperthermia at 38.5–39.5 °C / 101.3–103.1 °F in selected patients, never in week one.
Autonomic system
Vagus nerve stimulation, breathing retraining and orthostatic training at the pace your heart rate allows; hormone correction where needed.
Home protocol
Gut restoration and, in the last days, a written home protocol with pacing rules and follow-up laboratory dates.
Follow-up questions, from you or your doctor at home, go to the International Office.
How we treat ME/CFS, week by weekIs this program right for you?
The program fits you if
- You meet the ME/CFS criteria, whether the trigger was Epstein-Barr virus, Lyme disease, COVID-19 or an infection nobody identified
- Standard tests came back normal
- You can manage the trip and two to three weeks on a ward, even if you are housebound at home: the schedule is built around rest and a companion can stay
It is not the right place if
- You are fully bed-bound and cannot travel
- You have an untreated psychiatric emergency
- Your main problem is a condition that mimics ME/CFS and has its own treatment: untreated sleep apnea, uncontrolled thyroid disease, active cancer, severe anemia
If a physician reads your findings and thinks the program will not serve you, we say so before you book a flight. How a stay runs and how the cost overview is written: Long COVID and ME/CFS apheresis program.
Outpatient option
Cognitive symptoms in ME/CFS
For patients whose cognitive symptoms and sleep problems stand out, the Douwes Brain Center, the outpatient neuromodulation department of our hospital, offers an assessment of whether neuromodulation is suitable.
Evidence and limits
Evidence that ME/CFS has measurable biology is moderate and consistent. Evidence for the therapies is emerging, and no test yet shows which patient will respond, so we measure before the first session and again in week two.
Read the evidence in detail
The evidence that ME/CFS has measurable biology is moderate and consistent: reduced natural killer cell cytotoxicity has been found across many studies and confirmed by meta-analysis (Baraniuk, 2024), post-exertional symptoms separate patients from controls (Mateo et al., 2020), and metabolic profiling points to impaired pyruvate dehydrogenase function, a block in how cells burn fuel (Fluge et al., 2016). Peripheral endothelial dysfunction has also been measured in patients (Scherbakov et al., 2020).
The evidence for the therapies is emerging. Autoantibodies against β-adrenergic and muscarinic receptors were described in a subset of patients (Loebel et al., 2016); a pilot study removed them with immunoadsorption (Scheibenbogen et al., 2018), and a 2025 trial examined repeated immunoadsorption in post-COVID ME/CFS (Stein et al., 2025). For IHHT, NAD+ and hyperthermia in ME/CFS the evidence is limited to mechanism and small series. The studies cannot yet tell which patient will respond, so we measure before the first session and again in week two, and write each plan from the patient's own findings.
Where your treatment happens

The infusion room · Clinicum St. Georg 
A therapy room · Clinicum St. Georg 
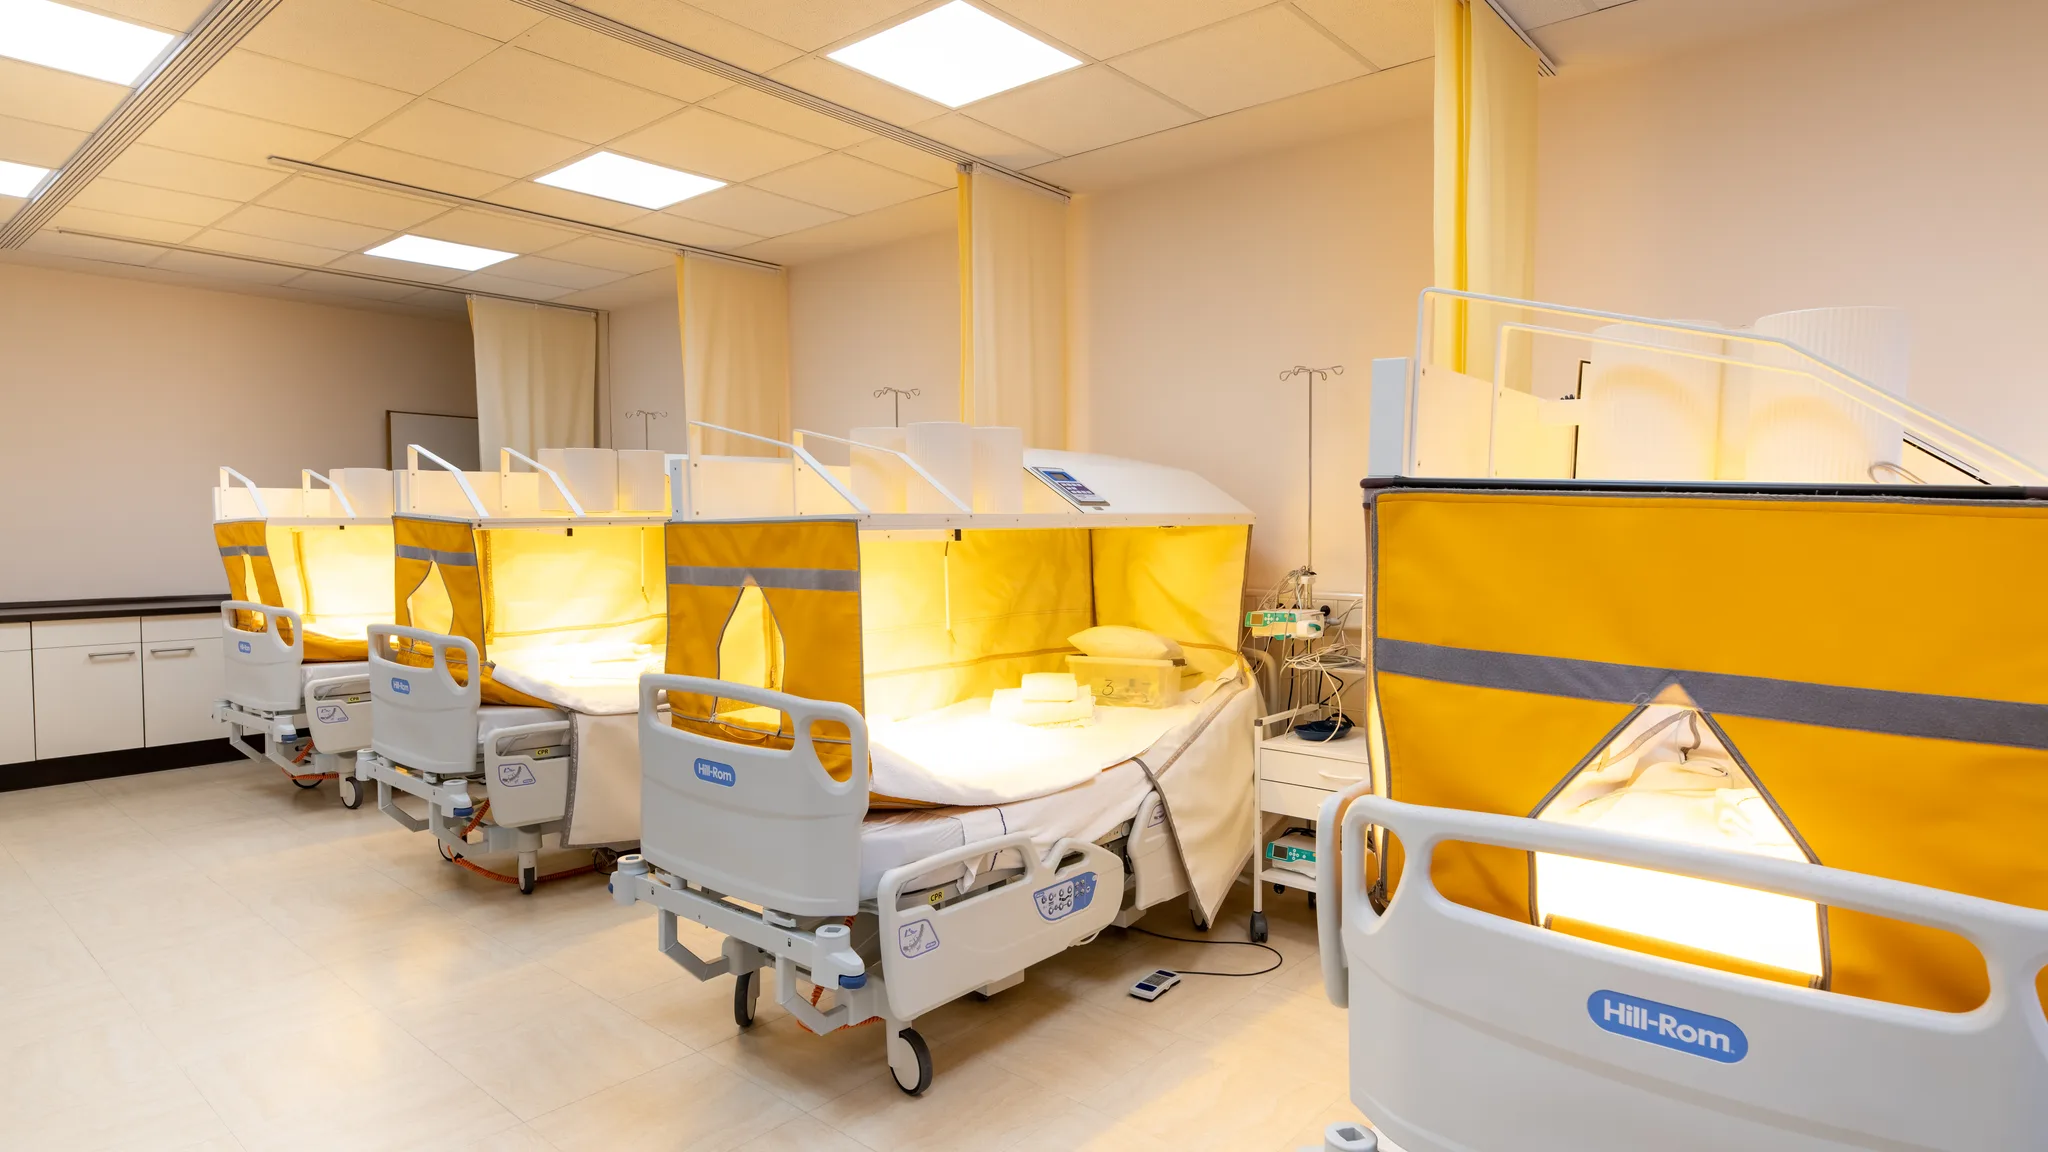
A patient room · Clinicum St. Georg
The laboratory and the diagnostics department are in the same building as the ward, so results reach your physician while you are still here.
Therapies
Treatments used in this program
- TherapyImmunoadsorption
Removes autoantibodies against adrenergic and muscarinic receptors from the plasma over a series of sessions.
- TherapyIHHT
Intermittent hypoxia-hyperoxia training, a seated session that trains the cells' oxygen handling.
- TherapyNAD+ infusion
Intravenous NAD+ for the energy metabolism, given slowly over several hours with a nurse present.
- TherapyHyperbaric oxygen (HBOT)
Pressurized oxygen sessions for patients with pronounced brain fog and poor tissue oxygenation.
- TherapyH.E.L.P. apheresis
Blood filtration for patients whose findings point to microclots and impaired microcirculation.
- TherapyImmune therapy
Thymus peptides and low-dose immunomodulation for the immune findings measured in the work-up.
From your first email to the flight home
The International Office handles your inquiry, records, travel and follow-up questions.
Step 1: Initial inquiry
A short message by online form, email or phone. The initial inquiry is free of charge.
Free of charge
Step 2: Reply from the International Office
The International Office reviews your message and your case directly and gets back to you.
Step 3: Secure transfer of records
After the first contact, the International Office requests your medical records and tells you how to send them securely.
Step 4: Medical review and video call
Your records are reviewed medically. A video call with a medically trained member of the International Office is free of charge; a video consultation with a physician is usually charged, and the International Office explains the fee before booking.
Video call with the International Office: free of charge
Step 5: Treatment proposal and cost overview
You receive an individual treatment proposal and an itemized cost overview in writing.
Step 6: Travel, stay and aftercare
The International Office helps you plan travel and your stay. You go home with detailed written plans for your doctor; follow-up questions go to the International Office.
Frequently asked questions about ME/CFS treatment
What is ME/CFS?
Myalgic encephalomyelitis/chronic fatigue syndrome is a multisystem illness in which exertion makes every symptom worse, often with a delay of a day or two. Fatigue that rest does not repair, unrefreshing sleep, cognitive slowing and problems standing upright belong to the picture. The 2015 Institute of Medicine report defines it by these features and treats it as a physical illness.
Is ME/CFS real?
Yes. Reduced natural killer cell function, autoantibodies against adrenergic and muscarinic receptors, impaired energy metabolism and endothelial dysfunction have been measured in patient groups, and the Institute of Medicine and the WHO classify it as a disease. A normal standard blood panel does not exclude it; the standard panel does not look at these systems.
How do you diagnose ME/CFS differently?
We apply the published criteria first, then measure the systems behind the symptoms: autoantibody and immune panels, mitochondrial and oxidative markers, orthostatic and heart-rate testing, screening for reactivated and persistent infections, hormones and gut markers. The point is a treatment plan written from your findings, with a baseline we can measure again in week two.
What treatments do you use for ME/CFS?
Depending on the findings: immunoadsorption or HELP apheresis for patients with elevated autoantibodies or microcirculation findings, IHHT and NAD+ infusions for the energy metabolism, immune therapy, mild whole-body hyperthermia, hormone correction and gut restoration. Therapies outside standard care are treatment attempts that your physician decides with you.
How long does the program take?
Two to three weeks as an inpatient. Severe ME/CFS can need a longer stay, and the physician will say so before you travel. Sessions are spaced with rest in between so that the program itself does not trigger post-exertional malaise. Some patients return for a second cycle after three to six months.
Is ME/CFS the same as burnout or depression?
No. Burnout and depression can share tiredness and poor concentration, but neither produces post-exertional malaise, and neither shows the immune and autonomic findings measured in ME/CFS. Antidepressants and graded exercise do not treat the mechanism, which is why so many patients arrive here after trying both.
Can I come if I am mostly housebound?
Often yes. The video consultation answers this: a physician looks at your current activity level, how you tolerate travel and whether the sessions in the plan can be run at the pace you need. Munich Airport is about 60 minutes by car, a companion can stay, and the ward schedule is built around rest.
What does the program cost?
After a physician has reviewed your findings, you receive a written, itemized cost overview: a package price plus individual add-ons. Treatment is self-pay; the itemized invoice can be submitted to a US insurer for out-of-network review.
Therapeutic plasma exchange within an individual plan
Therapeutic plasma exchange (TPE) is available for assessment across our condition programs, including longevity. Your physician checks the specific indication, risks and alternatives. Availability does not establish a benefit for every condition or a preventive anti-aging benefit.
Costs, in plain terms
- Self-pay: package price plus individual add-ons; no prices online.
- An itemized cost overview in writing before you travel; airport transfers are charged extra.
- No reimbursement promise; US patients can be put in touch with an independent US reimbursement office.
- Deposit before admission; the payment process is explained with your cost overview.
References
- Beyond myalgic encephalomyelitis/chronic fatigue syndrome: an IOM report on redefining an illness. JAMA 2015. PMID 25668027
- Myalgic encephalomyelitis: International Consensus Criteria. J Intern Med 2011. PMID 21777306
- Systematic review and meta-analysis of the prevalence of chronic fatigue syndrome/myalgic encephalomyelitis (CFS/ME). J Transl Med 2020. PMID 32093722
- Post-exertional symptoms distinguish Myalgic Encephalomyelitis/Chronic Fatigue Syndrome subjects from healthy controls. Work 2020. PMID 32568143
- Meta-analysis of natural killer cell cytotoxicity in myalgic encephalomyelitis/chronic fatigue syndrome. Front Immunol 2024. PMID 39483457
- Antibodies to β adrenergic and muscarinic cholinergic receptors in patients with Chronic Fatigue Syndrome. Brain Behav Immun 2016. PMID 26399744
- Immunoadsorption to remove ß2 adrenergic receptor antibodies in Chronic Fatigue Syndrome CFS/ME. PLoS One 2018. PMID 29543914
- Efficacy of repeated immunoadsorption in patients with post-COVID myalgic encephalomyelitis/chronic fatigue syndrome. Lancet Reg Health Eur 2025. PMID 39759581
- Metabolic profiling indicates impaired pyruvate dehydrogenase function in myalgic encephalopathy/chronic fatigue syndrome. JCI Insight 2016. PMID 28018972
- Peripheral endothelial dysfunction in myalgic encephalomyelitis/chronic fatigue syndrome. ESC Heart Fail 2020. PMID 32154656
From the journal
Reading on Long COVID, ME/CFS and post-viral fatigue
- ME/CFS & fatigue · · 7 min read
Latest treatment for chronic fatigue syndrome (ME/CFS): What the research shows
Told nothing can be done for ME/CFS? What has changed: the mechanisms now being targeted, the treatments being tested, and what we use in the clinic.
- ME/CFS & fatigue · · 7 min read
Chronic fatigue syndrome holistic treatment: A root-cause approach
Where do you start when every ME/CFS doctor has a different answer? How an integrative program looks at infections, mitochondria, immunity and the nervous system together.
- Mitochondrial health · · 8 min read
Mitochondrial dysfunction: Symptoms, causes, and treatment options
Why does one normal day cost you two in bed? How failing mitochondria produce that crash, the tests that show it, and what can be done about it.
Send a free inquiry
The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.
- Phone
- +49 8061 398-0
- Hours
- Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.
Munich Airport (MUC), about 60 minutes by car.