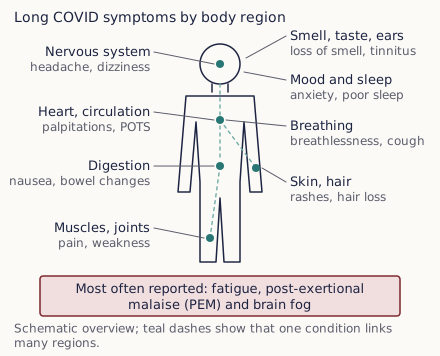
Post-COVID is the convergence of several related mechanisms rather than one disease. Research is still refining the picture; the following are the pathways with the most clinical relevance today, each with the studies that describe it.
Microclots & fibrinoid deposits
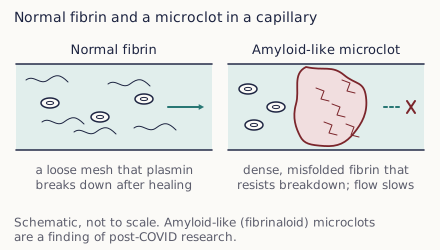
One of the most discussed findings in Post-COVID research is the presence of anomalous microclots in the blood of symptomatic patients. These are dense, amyloid-like fibrin structures that resist normal fibrinolysis, the body's clot-dissolving process (Pretorius et al., 2021; Kell et al., 2022).
The microclots trap inflammatory proteins, among them serum amyloid A, alpha-2 antiplasmin and complement fragments, as a proteomic analysis showed (Kruger et al., 2022). They obstruct capillary flow and reduce oxygen delivery to the tissues. Their detection is an emerging diagnostic marker, and their removal by apheresis is the rationale of the Long COVID and ME/CFS apheresis program.
Endothelial damage & vascular dysfunction
SARS-CoV-2 binds to ACE2 receptors on endothelial cells, the lining of every blood vessel, and damages them and their protective glycocalyx. Endothelial dysfunction and altered endothelial biomarkers persist in post-COVID patients and in ME/CFS (Haffke et al., 2022), and capillary density in the skin stays reduced months after the infection (Osiaevi et al., 2023).
Damaged endothelium loses its control of vessel width, promotes clotting and lets inflammatory molecules into the tissue. Endothelial repair is therefore a target of treatment next to microclot removal.
Viral persistence & reservoir theory
Fragments of the virus, including the spike protein, can persist long after the acute infection. Circulating spike protein has been found in the blood of patients with post-acute sequelae months after infection (Swank et al., 2023), and viral RNA has been detected in gut tissue and other reservoirs.
Persistent viral material can keep the immune system stimulated, drive chronic inflammation and sustain the endothelial damage. It is one explanation for the relapsing and remitting course some patients experience.
Immune dysregulation
In Long COVID patients we frequently see raised inflammatory cytokines, T-cell exhaustion and impaired NK cell function, reactivation of latent herpes viruses and autoantibodies against the patient's own tissues. Reactivation of Epstein-Barr virus has been linked to Long COVID and to its fatigue in two studies (Gold et al., 2021; Rohrhofer et al., 2023), and functional autoantibodies against G-protein coupled receptors have been described in patients with persistent symptoms (Wallukat et al., 2021).
Chronic immune activation feeds back on endothelial damage and microclot formation, as inflammatory mediators impair vascular function and the balance of coagulation.
Mitochondrial damage
SARS-CoV-2 affects the mitochondria, the organelles that produce the cell's energy. Impaired mitochondrial function means less ATP, more oxidative stress and compromised cellular respiration; a 2024 review sets out the mechanisms and the therapeutic approaches under study (Molnar et al., 2024).
This explains the fatigue, exercise intolerance and post-exertional malaise that characterize Long COVID. Impaired microcirculation compounds the problem by starving the mitochondria of oxygen and substrates; the mitochondrial page explains what is measured.
Autonomic dysfunction & the gut-brain axis
Postural orthostatic tachycardia syndrome and other autonomic disorders have been described after COVID-19 (Blitshteyn et al., 2021); they explain the racing pulse on standing and much of the exercise intolerance.
SARS-CoV-2 also infects gut epithelial cells. The resulting disruption of the microbiome, the intestinal barrier and the enteric nervous system contributes to gut symptoms and to systemic inflammation, and the gut-brain axis is one route to the brain fog and mood changes of Long COVID.