
Gut Restoration
Microbiome transfer
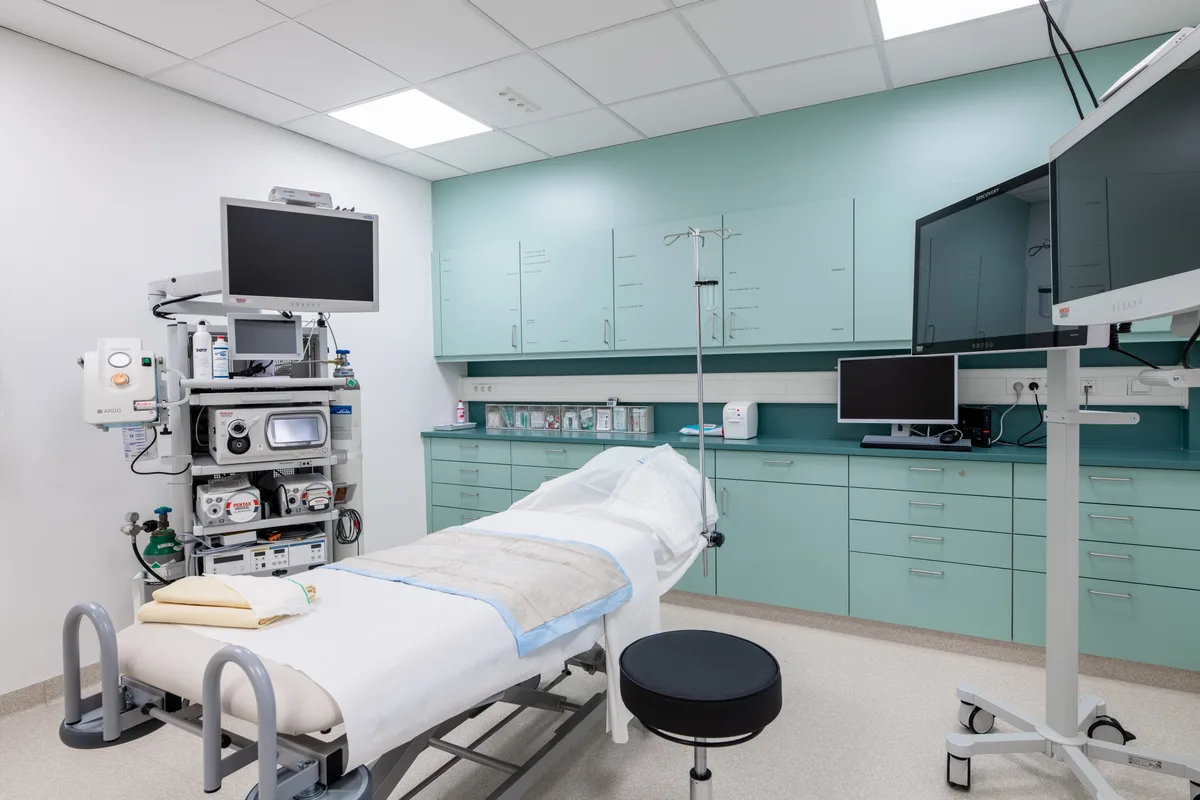
Microbiome transfer, or fecal microbiota transplantation, places processed stool from a screened healthy donor into a patient's intestine to re-establish a diverse microbial community. St. George Hospital performs it on the ward, after a gut work-up, as an inpatient procedure. The evidence is strong for recurrent C. difficile infection and emerging or limited for every other use.
What is microbiome transfer?
Microbiome transfer places the processed stool of a screened healthy donor into the intestine of a patient whose own microbial community has been depleted. The hospital uses it as part of the gut health program and within the functional medicine work-up, where a stool analysis has first shown what is missing. The medical term is fecal microbiota transplantation, FMT.
A healthy colon carries hundreds of bacterial species that ferment fiber into short-chain fatty acids, metabolize bile acids, occupy the niches a pathogen would otherwise take, and train the immune tissue in the gut wall. Long antibiotic courses, severe illness and some infections thin that community. A transfer does not add one strain, as a probiotic does. It replaces the whole ecosystem at once, which is why it works where capsules of single strains do not.
The transferred community settles over days to weeks. In the trial that established the method, the recipient's stool diversity moved towards the donor's within weeks of a single infusion (van Nood et al., N Engl J Med, 2013).

What conditions is it used for?
The hospital considers microbiome transfer for four groups of patients, and the strength of the evidence differs sharply between them.
- Recurrent Clostridioides difficile infection after at least two antibiotic failures. This is the established indication, and the evidence is strong.
- Severe intestinal dysbiosis after prolonged antibiotic therapy, including the months-long courses many Lyme disease patients have received before they arrive. Evidence here is limited.
- Persistent gastrointestinal symptoms during or after Lyme treatment, and gut dysbiosis documented in Long COVID or chronic fatigue. Evidence is limited.
- Inflammatory bowel conditions with documented microbial disruption, in cooperation with the treating gastroenterologist. Evidence is emerging for ulcerative colitis.
Outside recurrent C. difficile infection, microbiome transfer is an individual treatment attempt decided with the patient after medical consultation. The decision rests on a stool analysis, not on the diagnosis alone: a patient with a normal microbiome does not receive a transfer, whatever the label on the referral letter.
Who is excluded: patients with a severely weakened immune system, for example during chemotherapy or after transplantation; patients with acute severe colitis or recent bowel surgery; patients who cannot safely undergo bowel preparation or sedation; and patients with a documented severe allergy to a food the donor eats. Oncology patients are reviewed by Dr. Martin Rößner and the clinical team before any decision.
How a transfer runs on our ward
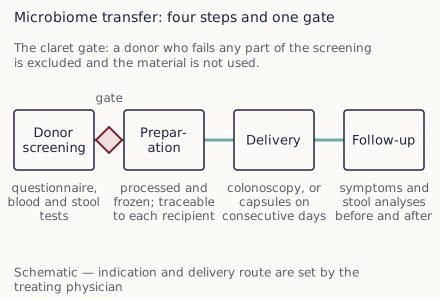
- Before admission, a stool analysis establishes your baseline: diversity, key species, calprotectin and short-chain fatty acids. If you are on antibiotics, they are stopped 48 hours before the transfer where this is medically possible.
- For colonoscopic delivery, you take a standard bowel preparation the evening before. For capsule delivery there is no preparation.
- Colonoscopic delivery takes 30 to 60 minutes under light sedation. The physician places the donor material in the right colon and terminal ileum. You wake on the ward and rest for the afternoon.
- Capsule delivery means swallowing coated capsules with water on consecutive days, under nursing supervision, with nothing else to do.
- For the first days, bloating, loose stool or mild cramping are common while the new community settles. Nurses record stool frequency and temperature twice daily; a physician sees you every morning.
- At six to eight weeks, a follow-up stool analysis is compared with the baseline. This is the measurement that tells us whether the transfer took hold.
Evidence and safety
For recurrent C. difficile infection the evidence is strong. In the first randomized trial, a single duodenal infusion of donor stool resolved the infection far more often than the standard vancomycin course, and the trial was stopped early because the difference was so large (van Nood et al., N Engl J Med, 2013). A Cochrane review of six randomized trials concluded that the transfer likely leads to a large increase in resolution compared with antibiotics in immunocompetent adults, while noting that the trials were too small to settle its safety profile (Minkoff et al., Cochrane Database Syst Rev, 2023).
For ulcerative colitis the evidence is emerging. An Australian trial of intensive, multidonor transfer achieved clinical remission and endoscopic improvement more often than placebo over eight weeks, and the authors described it as a promising option that still needs its dosing and donor matching defined (Paramsothy et al., Lancet, 2017).
For irritable bowel syndrome the trials disagree. A Norwegian colonoscopic trial found response in 65 percent of treated patients versus 43 percent on placebo at three months (Johnsen et al., Lancet Gastroenterol Hepatol, 2018), and a second Norwegian trial using a single well-characterized donor reported dose-dependent symptom improvement (El-Salhy et al., Gut, 2020). A Danish capsule trial found the opposite: the microbiome changed, but the placebo group felt better at three months (Halkjær et al., Gut, 2018). The lesson we draw is that donor, route and dose decide the result, which is why the hospital works with characterized donor lots and colonoscopic delivery wherever possible.
What the evidence does not show: no randomized trial has tested microbiome transfer in Lyme disease, Long COVID or chronic fatigue, and improvement in those conditions cannot be promised from the C. difficile data.
Safety rests on donor screening. The 2019 international consensus on stool banking sets the standard the hospital follows: donor questionnaire, blood serology, stool testing for pathogens and multidrug-resistant organisms, and traceable frozen lots (Cammarota et al., Gut, 2019), building on the earlier European practice consensus (Cammarota et al., Gut, 2017). The reason that screening is non-negotiable is documented: two patients in US trials developed bacteremia with an ESBL-producing E. coli traced to one donor, and one of them died (DeFilipp et al., N Engl J Med, 2019). Across published series, most adverse events are transient gastrointestinal symptoms; serious events were more frequent with lower-gastrointestinal routes and in sicker patients (Wang et al., PLoS One, 2016).
How it fits the program
A transfer is never the first step. The functional diagnostics and stool analysis come first, and the transfer is scheduled only when they show a depleted community that diet and targeted probiotics are unlikely to rebuild. In the gut health program it is combined with an anti-inflammatory, fiber-rich diet that feeds the new community, with immune therapy where the immune profile asks for it, and in selected cases with rectal ozone in the weeks before the transfer. Colon hydrotherapy is not combined with a transfer in the weeks after it, because the new community needs to stay in place.
For Lyme disease patients the transfer, when indicated, sits at the end of the antibiotic phase. For Long COVID and chronic fatigue patients it is one module within a two- to three-week inpatient stay whose core is elsewhere. See how a stay runs for the week-by-week shape.
Costs: a transfer is an add-on to the package price of your program and covers the donor material and its processing, the colonoscopy with sedation or the capsule course, and the two stool analyses. A deposit is paid before admission. A physician reads your findings and sends a written, itemized cost overview before you travel; details on billing and out-of-network claims are on costs and insurance, and the travel and coordinator steps on information for international patients.
Questions patients ask
Is microbiome transfer safe?
Does the procedure hurt?
Where does the donor material come from?
Can microbiome transfer treat Lyme disease, Long COVID or chronic fatigue?
How much does microbiome transfer cost?
How soon do I notice a change?
If a long antibiotic history or a stool analysis has left you with a gut that no longer works, write a short inquiry to the International Office, free of charge; it asks for your findings afterwards. A physician reads them before the video consultation and tells you whether a transfer belongs in your program.
References
- Duodenal infusion of donor feces for recurrent Clostridium difficile. N Engl J Med 2013. PMID 23323867
- Fecal microbiota transplantation for the treatment of recurrent Clostridioides difficile (Clostridium difficile). Cochrane Database Syst Rev 2023. PMID 37096495
- European consensus conference on faecal microbiota transplantation in clinical practice. Gut 2017. PMID 28087657
- International consensus conference on stool banking for faecal microbiota transplantation in clinical practice. Gut 2019. PMID 31563878
- Drug-Resistant E. coli Bacteremia Transmitted by Fecal Microbiota Transplant. N Engl J Med 2019. PMID 31665575
- Systematic Review: Adverse Events of Fecal Microbiota Transplantation. PLoS One 2016. PMID 27529553
- Multidonor intensive faecal microbiota transplantation for active ulcerative colitis: a randomised placebo-controlled trial. Lancet 2017. PMID 28214091
- Faecal microbiota transplantation versus placebo for moderate-to-severe irritable bowel syndrome: a double-blind, randomised, placebo-controlled, parallel-group, single-centre trial. Lancet Gastroenterol Hepatol 2018. PMID 29100842
- Efficacy of faecal microbiota transplantation for patients with irritable bowel syndrome in a randomised, double-blind, placebo-controlled study. Gut 2020. PMID 31852769
- Faecal microbiota transplantation alters gut microbiota in patients with irritable bowel syndrome: results from a randomised, double-blind placebo-controlled study. Gut 2018. PMID 29980607
Send a free inquiry
The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.
- Phone
- +49 8061 398-0
- Hours
- Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.
Munich Airport (MUC), about 60 minutes by car.