Close-up of hands holding an open navy folder with a few pages of unreadable printed results at a light oak desk

Hormone Optimization

Precision hormone diagnostics & bioidentical therapy for men

St. George Hospital runs a full male hormone panel before any prescription: total and free testosterone, SHBG, DHT, estradiol, DHEA-S, cortisol, thyroid and metabolic markers, drawn fasting in the morning and repeated when a single value could mislead. Where a deficiency matches your symptoms, we treat it with bioidentical testosterone and monitor hematocrit and PSA on a fixed schedule.

Is this you?

You are 48, you train, and the gym is not giving back what it used to.

Sleep is shallower. The belly fat arrived without an invitation. You are quicker to snap at people you love. A testosterone test came back "low-normal" and the conversation ended there, or ended with a prescription and no plan for what comes after. Hormone assessment is one part of our men's health program, and it starts with a panel read by a physician.

Understanding Male Hormonal Health

Hormonal decline is not inevitable suffering

From the mid-thirties, men produce gradually less testosterone, DHEA and growth hormone. The decline is slow in healthy men and faster with obesity, sleep apnea, type 2 diabetes, chronic illness and some medications. It is also happening across generations: a study of American men found serum testosterone falling from one birth cohort to the next, independent of age (Travison et al., Journal of Clinical Endocrinology and Metabolism, 2007). Fatigue, loss of muscle, abdominal fat, low mood, poor concentration and reduced libido are the symptoms; sometimes the cause is testosterone, sometimes it is the sleep apnea that lowered it.

Our program does not wait for a value to fall far below the reference range before looking, and it does not prescribe on a single value either. The panel below is drawn fasting in the morning, repeated if borderline, and read against your symptoms and your metabolic picture before a physician decides whether a hormone is the cause.

The program is supervised by Julian Douwes M.D. and Daniela Hudi M.D., with laboratory analysis through our laboratory and immune testing.

A middle-aged man seen from behind on a lakeside bench at a Bavarian lake
Rowing boat at a jetty in winter sun
Signs of Hormonal Imbalance

Recognizing andropause and hormonal decline

Men tend to file these symptoms under age, stress or work. Several of them are also the symptoms of depression, sleep apnea, hypothyroidism and iron overload, which is why the panel is wider than testosterone alone.

  • Persistent fatigue and reduced energy
  • Loss of muscle mass and increased body fat
  • Decreased libido and erectile function
  • Poor concentration or brain fog
  • Mood changes, irritability or depressive symptoms
  • Sleep disturbance, including snoring and unrefreshing sleep
  • Reduced exercise tolerance and slower recovery
  • Joint stiffness and reduced bone density
  • Abdominal fat and metabolic syndrome markers
  • Hair thinning or changes in body hair
What we test

The male hormone panel

The panel evaluates production, transport, metabolism and the systems that interact with testosterone. It is drawn between 07:00 and 09:00, fasting, on day one, and the testosterone fraction is repeated on day two when the first value is borderline. Physiological measurements (body composition, sleep screening, fitness test) belong to functional diagnostics and are read together with the blood work in the functional medicine consultation.

  1. Androgen panel. Total testosterone, free and bioavailable testosterone (calculated from SHBG and albumin), DHT and androstenedione, plus LH and FSH to tell testicular from pituitary causes.
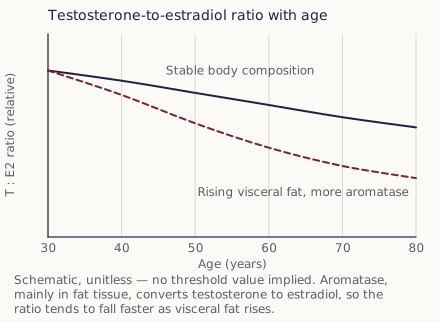
  2. Estrogen. Estradiol by a sensitive assay. Excess conversion of testosterone to estradiol (aromatization) rises with body fat and changes how replacement behaves.
  3. Adrenal hormones. DHEA-S, morning cortisol and, where the history points to it, a diurnal cortisol curve.
  4. Thyroid. TSH, free T3, free T4 and thyroid antibodies, because hypothyroidism copies most symptoms of low testosterone.
  5. Metabolic and safety markers. Fasting insulin, HbA1c, lipids, ferritin, vitamin D, hs-CRP, prolactin, full blood count with hematocrit, and PSA with a prostate examination before any testosterone is prescribed.
Line chart of the testosterone-to-estradiol ratio from age thirty to eighty, falling faster when visceral fat rises
Aromatase in fat tissue converts testosterone to estradiol, so the ratio falls faster as visceral fat rises. Schematic, not measured data.
How we treat

Individualized hormone optimization

From the results, the physician writes a plan that may include one or more of the components below. Testosterone is prescribed only for confirmed hypogonadism: symptoms plus a low morning testosterone on two occasions. The practical details of routes and monitoring are on the hormone therapy page.

Bioidentical testosterone

Transdermal gel or injectable testosterone, dosed to bring the value into the mid-normal range and no higher. Hematocrit and PSA are checked at baseline, after three to six months and then yearly; the dose is adjusted on symptoms and values together.

DHEA and pregnenolone

Precursor hormones of the adrenal cascade. We replace DHEA only when DHEA-S is clearly low and symptoms fit; in older men without a deficiency the evidence that it helps is limited.

Thyroid optimization

Where the panel shows hypothyroidism, levothyroxine or, in selected cases, a T4/T3 combination. Treating the thyroid first often changes what the testosterone values look like six weeks later.

Aromatase and body composition

Estradiol that is high relative to testosterone is addressed first through fat loss, zinc repletion and, where needed, a change in testosterone route or dose. Aromatase-inhibitor drugs are not used routinely in men because of their effect on bone.

Metabolic and lifestyle support

Insulin sensitivity, sleep apnea treatment, resistance training, protein intake, vitamin D and magnesium. In some men these raise testosterone enough that replacement is not needed, which is the better outcome.

Evidence and limits

Testosterone therapy relieves symptoms in men with confirmed hypogonadism, and that evidence is strong. Without a clear deficiency it is limited: no trial shows better energy, cognition or longevity at normal or low-normal values.

Read the evidence in detail

The evidence that testosterone therapy relieves symptoms in men with confirmed hypogonadism is strong. In the Testosterone Trials, 790 men aged 65 and older with a serum testosterone below 275 ng/dL and symptoms received testosterone gel or placebo for one year. Treatment raised testosterone into the mid-normal range of young men and improved sexual activity, sexual desire and erectile function; the effect on walking distance was significant only when all participants were analyzed together (Snyder et al., New England Journal of Medicine, 2016). The Endocrine Society guideline builds on these and earlier trials: diagnose only with symptoms and two low morning values, treat with the aim of mid-normal levels, and monitor hematocrit and PSA (Bhasin et al., Journal of Clinical Endocrinology and Metabolism, 2018).

The evidence on cardiovascular safety is now strong. The TRAVERSE trial randomized men with hypogonadism and pre-existing or high cardiovascular risk to testosterone gel or placebo, with a mean follow-up of 33 months. A major adverse cardiac event occurred in 7.0% of the testosterone group and 7.3% of the placebo group, meeting the non-inferiority criterion. Atrial fibrillation, pulmonary embolism and acute kidney injury were more frequent with testosterone (Lincoff et al., New England Journal of Medicine, 2023). Those three findings are why we screen for arrhythmia, clotting risk and kidney function before prescribing.

The evidence for DHEA and for low-dose testosterone in men without clear deficiency is limited. A two-year placebo-controlled trial in elderly men found no physiologically relevant benefit of either on body composition, physical performance, insulin sensitivity or quality of life (Nair et al., New England Journal of Medicine, 2006).

What the evidence does not show: no trial has shown that testosterone therapy in men with normal or low-normal values improves energy, cognition or longevity.


Your stay

How hormone assessment fits a stay

Day one: fasting panel at 07:00 to 09:00, prostate examination, body composition and sleep screening. Day two: repeat testosterone if borderline, results discussion when the laboratory reports. If replacement is indicated it starts on the ward, so that the first response and any side effects are seen by a physician before you travel. At discharge you receive the prescription, the monitoring schedule (hematocrit and PSA at three to six months, then yearly) and a letter for your own physician.

Three articles from our journal go deeper: a medical guide to hormone replacement therapy for men, why the testosterone-to-estrogen balance matters, and progesterone in men.

Costs and billing

Costs are individual: a package price plus individual add-ons. After a physician has reviewed your findings, you receive a written, itemized cost overview: a package price plus individual add-ons. Treatment is self-pay; the invoice is itemized in English with diagnoses and procedure descriptions for out-of-network review. See Costs and insurance and, for the video consultation before you travel, Information for international patients.

Related pages

  • About the conditionMen's health program

    The hub: hormones, prostate and urinary function assessed in one stay.

  • About the conditionProstate health

    PSA, imaging and treatment options for benign enlargement and prostate cancer.

  • About the conditionUrinary function

    Frequency, urgency, nocturia and weak stream: how we find the cause.

  • TherapyHormone therapy

    Routes, doses, monitoring schedule and contraindications for bioidentical replacement.

  • About the conditionHormone optimization for longevity

    Thyroid, adrenal and sex hormones in the longevity program, for men and women.

  • TherapyNAD+ IV therapy

    Used alongside hormone therapy when mitochondrial markers and energy are low.

FAQ

Questions men ask about hormone therapy

Is testosterone therapy safe for the heart?

The TRAVERSE trial followed men with hypogonadism and high cardiovascular risk for about three years and found that testosterone gel was non-inferior to placebo for major cardiac events. It also found more atrial fibrillation, pulmonary embolism and acute kidney injury in the testosterone group. We screen for these risks before and during therapy.

What counts as low testosterone?

Endocrine guidelines require symptoms plus an unequivocally low morning total testosterone on at least two occasions, with free testosterone checked when SHBG is abnormal. A single low-normal value after a bad night is not a diagnosis. We repeat the sample on the ward under the same conditions before deciding.

Does testosterone cause prostate cancer?

Randomized trials to date have not shown that testosterone replacement at physiological doses causes prostate cancer, but it is not given to men with known prostate cancer, a PSA above 4 ng/mL, or an abnormal prostate examination. PSA and a digital examination are part of the baseline and of every follow-up.

Will I have to stay on it for life?

Not necessarily. Testosterone suppresses your own production while you take it, so stopping needs a plan. Weight loss, sleep apnea treatment, resistance training and correcting thyroid or iron problems raise testosterone in some men enough to stop. We review the need at each follow-up rather than renewing by default.

What does hormone optimization cost?

Costs are individual: a package price plus individual add-ons. After a physician has reviewed your findings, you receive a written, itemized cost overview: a package price plus individual add-ons. Treatment is self-pay; the invoice is itemized in English with diagnoses and procedure descriptions for out-of-network review.

If you have a testosterone result already, send it with the time of day it was drawn and a short history. A physician reads it before the video consultation and tells you whether a repeat panel or a therapy is the next step.

References

  1. Cardiovascular Safety of Testosterone-Replacement Therapy. New England Journal of Medicine 2023. PMID 37326322
  2. Effects of Testosterone Treatment in Older Men. New England Journal of Medicine 2016. PMID 26886521
  3. Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology and Metabolism 2018. PMID 29562364
  4. A population-level decline in serum testosterone levels in American men. Journal of Clinical Endocrinology and Metabolism 2007. PMID 17062768
  5. DHEA in elderly women and DHEA or testosterone in elderly men. New England Journal of Medicine 2006. PMID 17050889

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry