A middle-aged man seen from behind on a lakeside bench at a Bavarian lake

Prostate Health

Integrative prostate diagnostics & treatment

St. George Hospital evaluates the prostate beyond a single PSA value, with a laboratory panel, transrectal ultrasound and flow measurement, and treats benign enlargement, chronic prostatitis and prostate cancer with anti-inflammatory protocols and hormonal and immune support, in coordination with your urologist. This page explains what we test, what we treat, and where the evidence stands.

Is this you?

Twice a night, then three times, and now you plan the drive around it.

The urologist checked your PSA and either said “let’s watch it” or scheduled a biopsy. Neither felt like an answer. You would like to understand what is enlarged, what is inflamed, and what your real options are before anything gets cut or burned.

Understanding prostate health

Beyond PSA: what a prostate assessment here looks at

Prostate conditions affect most men over 50. Benign enlargement narrows the urethra and changes how the bladder empties; chronic prostatitis causes pelvic pain for months; prostate cancer is found or excluded in the same work-up. St. George Hospital evaluates all three together, because the symptoms overlap and a single PSA value cannot separate them.

The histological facts set the scale. In an analysis of more than 1,000 prostates from ten studies, benign prostatic hyperplasia was present in about 8 percent of men in their forties and in half of men aged 51 to 60, with the prevalence rising further with age (Berry et al., J Urol, 1984). Enlargement in tissue does not always mean symptoms, and symptoms do not always come from enlargement, which is why the assessment measures function as well as size.

For benign enlargement, chronic prostatitis and prostate cancer the hospital offers treatment that aims to preserve urinary and sexual function wherever possible. Where a condition calls for surgery or radiotherapy, the physicians say so and coordinate with your urologist; a confirmed cancer is treated in the prostate cancer program, alongside the treatment your urologist plans.

A person in a soft knit sweater sits by a tall window of a Bavarian guesthouse
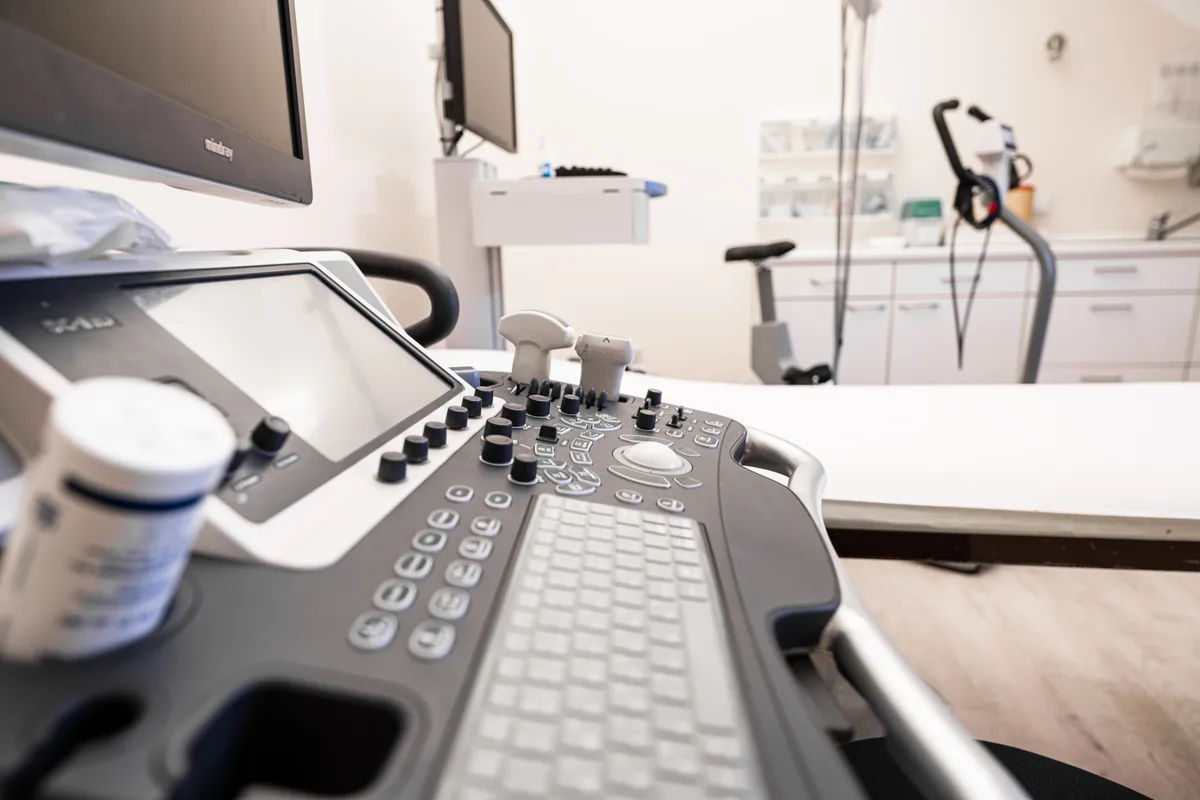
Close view of an ultrasound console keyboard and control panel
Ultrasound diagnostics Clinicum St. Georg
Conditions we treat

Three prostate conditions, three different aims

Benign prostatic hyperplasia (BPH)

Non-cancerous enlargement that causes frequency, nocturia, a weak stream and incomplete emptying. Standard care is an alpha-blocker, a 5-alpha-reductase inhibitor or both; the MTOPS trial found the combination reduced the risk of clinical progression by two thirds compared with placebo, and each drug alone by about a third (McConnell et al., N Engl J Med, 2003). The hospital works with that medication where you take it and adds the hormonal, inflammatory and local measures below.

Chronic prostatitis / chronic pelvic pain syndrome

The NIH classification separates acute and chronic bacterial prostatitis from category III, chronic prostatitis / chronic pelvic pain syndrome, and category IV, inflammation without symptoms (Krieger et al., JAMA, 1999). Category III is pelvic, perineal or genital pain without evidence of urinary infection, often with urgency, frequency and a poor stream (Schaeffer, Int J Antimicrob Agents, 2008). Antibiotics help only when cultures find bacteria.

Prostate cancer

Found or excluded in the work-up on this page, then treated in the oncology program alongside surgery, radiotherapy or hormone therapy, with immune support and supportive care coordinated with your urologist.

How we treat prostate cancer
What we test

The prostate assessment, step by step

StepWhat is measuredWhat it tells the physician
1. Laboratory panelPSA (total, free, ratio), testosterone, DHT, estradiol, SHBG, CRP, IL-6, urinalysis and culture, immune profileWhether the PSA pattern points to cancer or to benign disease, whether inflammation or a hormonal shift is driving the symptoms. In the prospective multicenter study that established the method, a free-to-total PSA ratio of 25 percent or less detected almost all cancers while sparing one in five men an unnecessary biopsy (Catalona et al., JAMA, 1998). Our laboratory and immune testing page lists the panels.
2. ImagingTransrectal ultrasound with volume measurement, elastography where indicated, bladder wall and post-void residual volumeGland size, suspicious areas, how much urine stays behind after voiding
3. FunctionUroflowmetry, International Prostate Symptom Score (IPSS), bladder diary, quality-of-life questionHow obstructed the flow is and how much the symptoms cost you day to day; these are the values we measure again after treatment
4. The written planReview of all findings with you, in person or by videoWhich of the three conditions is present, what the hospital recommends, and what belongs with your urologist

Urinary symptoms that do not come from the prostate, such as an overactive bladder or a neurological cause, are assessed on the page for urinary function in men.

Treatment options

How the hospital treats prostate conditions

Anti-inflammatory protocols for prostatitis

For category III prostatitis the plan combines anti-inflammatory infusions, phytotherapy, pelvic floor physiotherapy, dietary measures and, where cultures are positive, targeted antibiotics. The aim is the symptom score and the pain score, measured at the start and again in week two.

Hormone balancing

The laboratory measures testosterone, DHT, estradiol and SHBG. Where the ratio of estradiol to testosterone is shifted or DHT is high, the physician adjusts it with bioidentical and nutritional measures, in coordination with any 5-alpha-reductase inhibitor your urologist prescribes.

What hormone therapy involves

Immune support and regeneration

Thymus peptides, mistletoe and high-dose vitamin C infusions where the immune profile suggests it, and platelet-rich plasma for pelvic tissue regeneration in selected patients. Both are supportive measures with limited evidence in prostate disease, and the hospital says so.

What the evidence shows, and what it does not

Standard medication for benign enlargement rests on strong evidence. Supportive measures do not replace the treatment your urologist recommends for obstruction.

Read the evidence in detail

Evidence is graded on this page in four words: strong, moderate, emerging and limited. Standard medication for benign enlargement: strong (the MTOPS trial above). Heat for benign enlargement: moderate for transurethral microwave thermotherapy, the urological procedure that heats the gland from inside the urethra to high temperatures; a Cochrane review of 15 trials in 1,585 men found symptom scores fell by about two thirds with microwave thermotherapy and by about three quarters with transurethral resection, with resection giving the larger gain in flow (Hoffman et al., Cochrane Database Syst Rev, 2012). These results describe urological procedures and are not evidence for the supportive measures offered here.

Chronic prostatitis / chronic pelvic pain syndrome: the evidence for any single treatment is limited, and the physicians combine measures and measure the symptom score rather than promise a result. What the evidence does not show is that hormonal measures shrink a benign prostate in a controlled trial, and the hospital does not claim that they do.


Costs and billing

Treatment at St. George Hospital is self-pay. Costs are individual: a package price plus individual add-ons, set out in a written, itemized cost overview after a physician has read your findings. A deposit is paid before admission. After the stay you receive an itemized invoice in English that you can submit to your insurer; reimbursement is not promised. Details are on costs and insurance.

Traveling here

Patients from more than 60 countries have been treated here. Munich Airport is about 60 minutes by car; the International Office arranges the transfer (charged extra) and the video consultation before you travel, and a prostate assessment can be combined with the hormone optimization work-up in the same days. The practical side is under information for international patients.

FAQ

Questions men ask about prostate assessment and treatment

Is a raised PSA the same as prostate cancer?

No. PSA rises with benign enlargement, inflammation, recent ejaculation or cycling, and with cancer. The share of free PSA helps: in the multicenter study that established the method, a free-to-total ratio of 25 percent or less flagged almost all cancers while sparing one in five men an unnecessary biopsy. The hospital reads the ratio, the trend over time and the ultrasound together before advising a biopsy.

What is chronic prostatitis, and is it an infection?

Usually not. The NIH classification separates acute and chronic bacterial prostatitis, which are infections, from category III, chronic prostatitis / chronic pelvic pain syndrome, which is pelvic or perineal pain for months without evidence of urinary infection. Category III is by far the most common form. Antibiotics help only when a bacterial cause is found, which is why the work-up includes cultures before any treatment.

Do you treat prostate cancer on this page?

The work-up on this page is where prostate cancer is found or excluded. Treatment of a confirmed cancer runs in the oncology program, alongside the surgery, radiotherapy or hormone therapy your urologist plans, and is described on the prostate cancer page. The two pages share the same laboratory panel and the same physicians.

Will treatment affect urinary or sexual function?

Preserving both is the stated aim of every plan here. Hormonal and anti-inflammatory measures do not carry the risk of incontinence or erectile dysfunction that surgery and radiotherapy carry, and the physician discusses what each option means for you before you consent.

How much does a prostate assessment cost?

This page lists no prices. After a physician has reviewed your findings, you receive a written, itemized cost overview: a package price plus individual add-ons. Nothing is booked before you have it. Details are on costs and insurance.

If you want the assessment, send your PSA history, any biopsy or imaging reports and a note of your symptoms. A physician reads them before the video consultation and tells you in writing what the work-up here would add.

References

  1. The development of human benign prostatic hyperplasia with age.. J Urol 1984. PMID 6206240
  2. Use of the percentage of free prostate-specific antigen to enhance differentiation of prostate cancer from benign prostatic disease: a prospective multicenter clinical trial.. JAMA 1998. PMID 9605898
  3. NIH consensus definition and classification of prostatitis.. JAMA 1999. PMID 10422990
  4. Epidemiology and evaluation of chronic pelvic pain syndrome in men.. Int J Antimicrob Agents 2008. PMID 18164597
  5. The long-term effect of doxazosin, finasteride, and combination therapy on the clinical progression of benign prostatic hyperplasia.. N Engl J Med 2003. PMID 14681504
  6. Microwave thermotherapy for benign prostatic hyperplasia.. Cochrane Database Syst Rev 2012. PMID 22972068

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry