


Is this you?

"Everyone is tired." Not like this.

You have stopped explaining it, because the explanation sounds like complaining. Your calendar is a list of things you canceled. A friend says you look well, and from the outside you do. Inside, a shower is a decision that costs the afternoon.

This page sets out what ME/CFS is, biologically, why it is neither depression nor deconditioning, and where the ME/CFS program at St. George Hospital starts. "It is psychological" is a sentence about the limits of the tests that were run, not about you.

Bedroom window with a half-drawn curtain and a cup on the sill
More Than Tiredness

What is ME/CFS?

Myalgic encephalomyelitis / chronic fatigue syndrome is a chronic illness in which the body cannot sustain normal activity. The 2015 report of the US Institute of Medicine defines it by a substantial reduction in the ability to work, study or live as before for at least six months, profound fatigue, post-exertional malaise and unrefreshing sleep, together with cognitive impairment or orthostatic intolerance (Clayton, 2015). The International Consensus Criteria describe the same illness in more detail for clinicians (Carruthers et al., 2011); how we apply them is on the diagnosis page.

What distinguishes ME/CFS from ordinary tiredness is post-exertional malaise: a worsening of all symptoms after even minor physical or mental effort, often a day later and lasting days. A short walk can mean three days in bed; one hour of reading can cost a week of concentration. Post-exertional symptoms separate ME/CFS patients from healthy controls in formal testing (Mateo et al., 2020).

The World Health Organization classifies the illness as a neurological disease (ICD-11 code 8E49). A meta-analysis of prevalence studies puts it at under one percent of the population by the stricter clinical definitions, which still makes it common (Lim et al., 2020).

Abstract teal and navy visual
The biology

Is ME/CFS real?

Yes. The question is asked because the routine tests come back normal, and the answer is in the tests that are not routine. Natural killer cells, the immune cells that clear infected cells, have reduced cytotoxicity in ME/CFS patients across studies, as a 2024 meta-analysis confirms (Baraniuk et al., 2024). Autoantibodies against adrenergic and muscarinic receptors, which regulate circulation and the autonomic nervous system, are raised in a subset of patients (Loebel et al., 2016). Immune cells produce less energy on demand (Tomas et al., 2017); the mitochondrial page sets out that research. The lining of the small blood vessels functions poorly, which is measurable in the forearm (Scherbakov et al., 2020). The gut microbiome of patients lacks butyrate-producing bacteria in a pattern that tracks with fatigue (Guo et al., 2023).

The evidence that these findings exist is strong; the evidence on which of them drives the illness in a given patient is still emerging. None is a single diagnostic test. That is the reason the work-up at St. George Hospital measures all of them rather than picking one, and the reason the treatment plan differs from patient to patient.

Origins

What causes ME/CFS?

Usually a trigger in a person with an underlying susceptibility, and the best documented triggers are infections. In a prospective cohort of college students, a share of those who developed infectious mononucleosis met ME/CFS criteria six months later (Jason et al., 2021); the same group had shown orthostatic intolerance in adolescents after mononucleosis a decade earlier (Katz et al., 2012). The pandemic added SARS-CoV-2 to the list: the major review of Long COVID describes the overlap with ME/CFS and the shared mechanisms (Davis et al., 2023).

Viral infections

Epstein-Barr virus, cytomegalovirus, enteroviruses, HHV-6 and SARS-CoV-2 are the most common infectious triggers. ME/CFS has been documented after many different viral infections, and Long COVID has raised the number of patients worldwide.
Bacterial infections

Lyme disease and its co-infections are a recognized trigger. Many patients first labeled with post-treatment Lyme disease syndrome meet the full criteria for ME/CFS, which points to shared mechanisms.

Immune dysfunction

Reduced natural killer cell function, shifted T-helper ratios, raised pro-inflammatory cytokines and mast cell activation are found in patient groups. The immune system appears stuck in low-grade activation.

Mitochondrial failure

Reduced ATP production, raised oxidative stress and an impaired response to exertion are hallmarks. The cells cannot produce enough energy for the body's demands, which explains the fatigue and the post-exertional malaise.

Autonomic dysfunction

The autonomic nervous system, which controls heart rate, blood pressure, digestion and temperature, misfires in most patients. This explains the orthostatic intolerance, POTS and exercise intolerance patients report.

Gut dysbiosis

An altered gut microbiome, increased intestinal permeability and a disrupted gut-brain axis feed systemic inflammation, immune activation and neurological symptoms. The gut is part of the work-up.

Why tests miss it

Why standard tests come back "normal"

One of the most frustrating parts of ME/CFS is that the standard tests, complete blood count, basic metabolic panel, thyroid function, routine imaging, return normal results. Many physicians conclude from that that nothing is wrong.

The problem is that the standard tests do not look in the right places. ME/CFS involves dysfunction at the cellular and immunological level that specialized testing can show:

  • Mitochondrial function testing (ATP profile, organic acids) is not part of a standard work-up
  • Detailed immune panels (NK cell function, cytokine profiles) are rarely ordered
  • Chronic infection markers (EBV reactivation, Lyme persistence) need specialized interpretation
  • Autonomic function testing is seldom available in primary care
  • Gut permeability and microbiome analysis are not standard laboratory tests
  • Exertion testing: a two-day cardiopulmonary exercise test shows the drop in performance on the second day that is characteristic of post-exertional malaise (Lim et al., 2020), and is used only when a patient can tolerate it

At St. George Hospital the diagnostic protocol targets these systems. We look for what the standard panel does not measure, and we repeat the measurements in the second week of the stay.

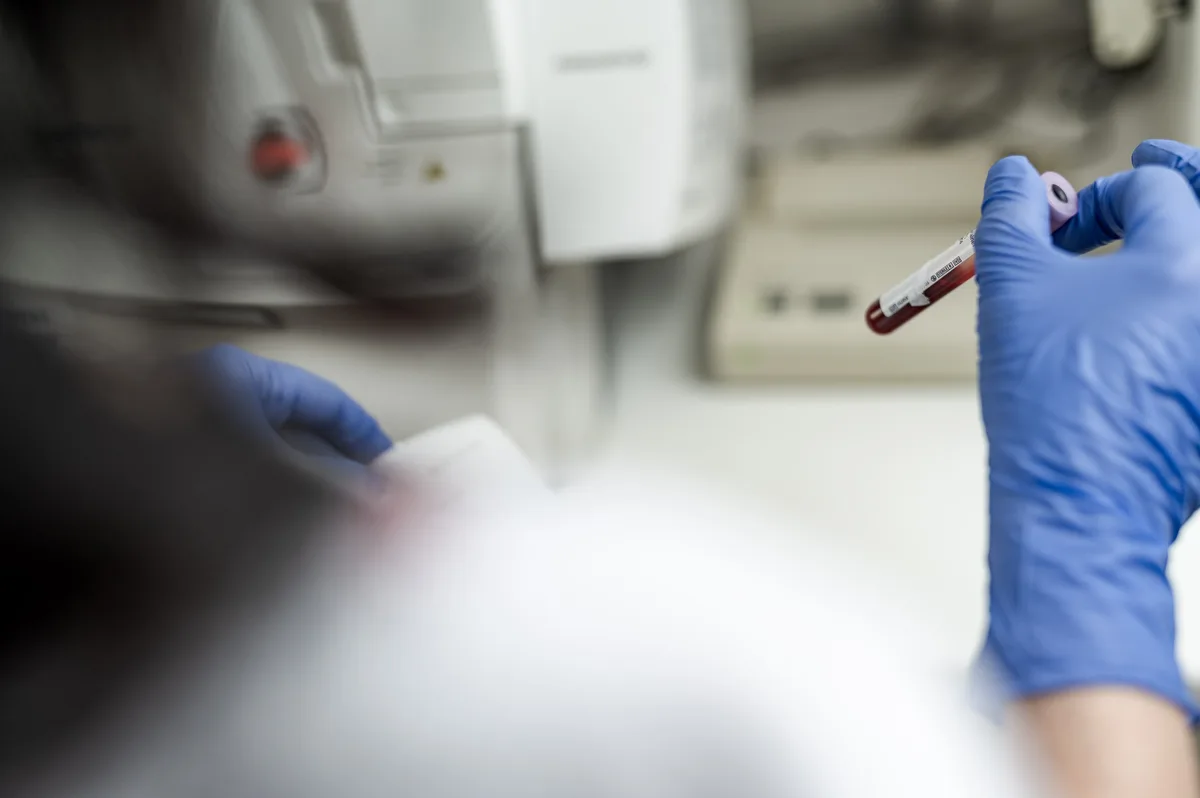
A gloved hand holding a blood sample tube in a laboratory
A blood sample in the clinic laboratory. Clinicum St. Georg
What helps now

What can be done before treatment starts?

Pacing: staying inside the energy you have on a given day, rather than pushing through and paying for it, is the one management approach with support in the literature, and a scoping review draws out the lessons for Long COVID (Sanal-Hayes et al., 2023). Graded exercise that ignores post-exertional malaise is not advised. Record what triggers a crash and how long it lasts; that record is the first thing a physician here reads, and it decides how the stay is paced.

What the hospital adds is the inpatient setting: a two to three week stay in which the work-up, the treatment program and the rest between sessions are planned around your tolerance. For patients from abroad this runs inside the Long COVID and ME/CFS apheresis program, with a video consultation in English before you travel and the flight from Munich Airport an hour away by car. Therapies outside standard care, such as apheresis or immunoadsorption for ME/CFS, are individual treatment attempts, decided with you after medical consultation from the findings.

FREQUENTLY ASKED QUESTIONS

Common questions about ME/CFS

What is ME/CFS?

Myalgic encephalomyelitis / chronic fatigue syndrome is a chronic multi-system illness. The 2015 US Institute of Medicine criteria require a substantial reduction in the ability to work, study or live as before for at least six months, with profound fatigue, post-exertional malaise and unrefreshing sleep, plus cognitive impairment or orthostatic intolerance. The World Health Organization lists it as a neurological disease.

Is ME/CFS real?

Yes. Reduced natural killer cell function, autoantibodies against adrenergic and muscarinic receptors, impaired cellular energy production, endothelial dysfunction and a disturbed gut microbiome have each been documented in patient groups compared with healthy controls. None is a single diagnostic test yet; together they describe an organic illness.

What causes ME/CFS?

Usually a trigger in a susceptible person. The best documented triggers are infections: Epstein-Barr virus, SARS-CoV-2, enteroviruses, Lyme disease and its co-infections. A prospective study of college students found that a share of those who developed infectious mononucleosis met ME/CFS criteria six months later. The illness then runs on immune, metabolic and autonomic mechanisms that outlast the infection.

Is ME/CFS the same as Long COVID?

They overlap. A proportion of Long COVID patients meet ME/CFS criteria, and the mechanisms described in both, post-exertional malaise, endothelial dysfunction, microclots, autoantibodies and mitochondrial impairment, are largely shared. At St. George Hospital the two are treated in one program, written from each patient's findings rather than from the label.

Can ME/CFS get better?

The course varies widely between patients, and no treatment has shown a guaranteed result. What can be done is to find the mechanisms active in you, treat them, and measure the change: the markers from the work-up are repeated in the second week of the program, and the plan at home is written from them. We discuss what is realistic for your history in the first consultation.

Next step

Where to go from here

Knowing what the illness is comes first. The next step is a medical team that measures the mechanisms and treats what it finds.

Related therapies

Therapies used in our ME/CFS program

IHHT oxygen therapy

Targets the mitochondrial side of ME/CFS by stimulating the formation of new mitochondria through controlled changes in oxygen.

What IHHT training involves →

Immunoadsorption

Removes the autoantibodies against adrenergic and muscarinic receptors found in a subset of patients; an individual treatment attempt with emerging evidence.

What immunoadsorption involves →

References

  1. Beyond myalgic encephalomyelitis/chronic fatigue syndrome: an IOM report on redefining an illness. JAMA 2015. PMID 25668027
  2. Myalgic encephalomyelitis: International Consensus Criteria. J Intern Med 2011. PMID 21777306
  3. Systematic review and meta-analysis of the prevalence of chronic fatigue syndrome/myalgic encephalomyelitis (CFS/ME). J Transl Med 2020. PMID 32093722
  4. Risks for Developing Myalgic Encephalomyelitis/Chronic Fatigue Syndrome in College Students Following Infectious Mononucleosis: A Prospective Cohort Study. Clin Infect Dis 2021. PMID 33367564
  5. Long COVID: major findings, mechanisms and recommendations. Nat Rev Microbiol 2023. PMID 36639608
  6. Meta-analysis of natural killer cell cytotoxicity in myalgic encephalomyelitis/chronic fatigue syndrome. Front Immunol 2024. PMID 39483457
  7. Antibodies to β adrenergic and muscarinic cholinergic receptors in patients with Chronic Fatigue Syndrome. Brain Behav Immun 2016. PMID 26399744
  8. Cellular bioenergetics is impaired in patients with chronic fatigue syndrome. PLoS One 2017. PMID 29065167
  9. Peripheral endothelial dysfunction in myalgic encephalomyelitis/chronic fatigue syndrome. ESC Heart Fail 2020. PMID 32154656
  10. Deficient butyrate-producing capacity in the gut microbiome is associated with bacterial network disturbances and fatigue symptoms in ME/CFS. Cell Host Microbe 2023. PMID 36758522
  11. Post-exertional symptoms distinguish Myalgic Encephalomyelitis/Chronic Fatigue Syndrome subjects from healthy controls. Work 2020. PMID 32568143
  12. The Prospects of the Two-Day Cardiopulmonary Exercise Test (CPET) in ME/CFS Patients: A Meta-Analysis. J Clin Med 2020. PMID 33327624
  13. Orthostatic tolerance testing in a prospective cohort of adolescents with chronic fatigue syndrome and recovered controls following infectious mononucleosis. Clin Pediatr (Phila) 2012. PMID 22850676
  14. A scoping review of 'Pacing' for management of Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS): lessons learned for the long COVID pandemic. J Transl Med 2023. PMID 37838675

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry