
Systemic Hyperthermia
Whole-body hyperthermia
Whole-body hyperthermia raises the core body temperature to 38.5–42 °C / 101.3–107.6 °F under continuous medical monitoring, inside an inpatient program. St. George Hospital uses it in chronic Lyme disease with intravenous antibiotics, alongside oncology treatment, and in a mild form in ME/CFS and Long COVID.
What is whole-body hyperthermia?
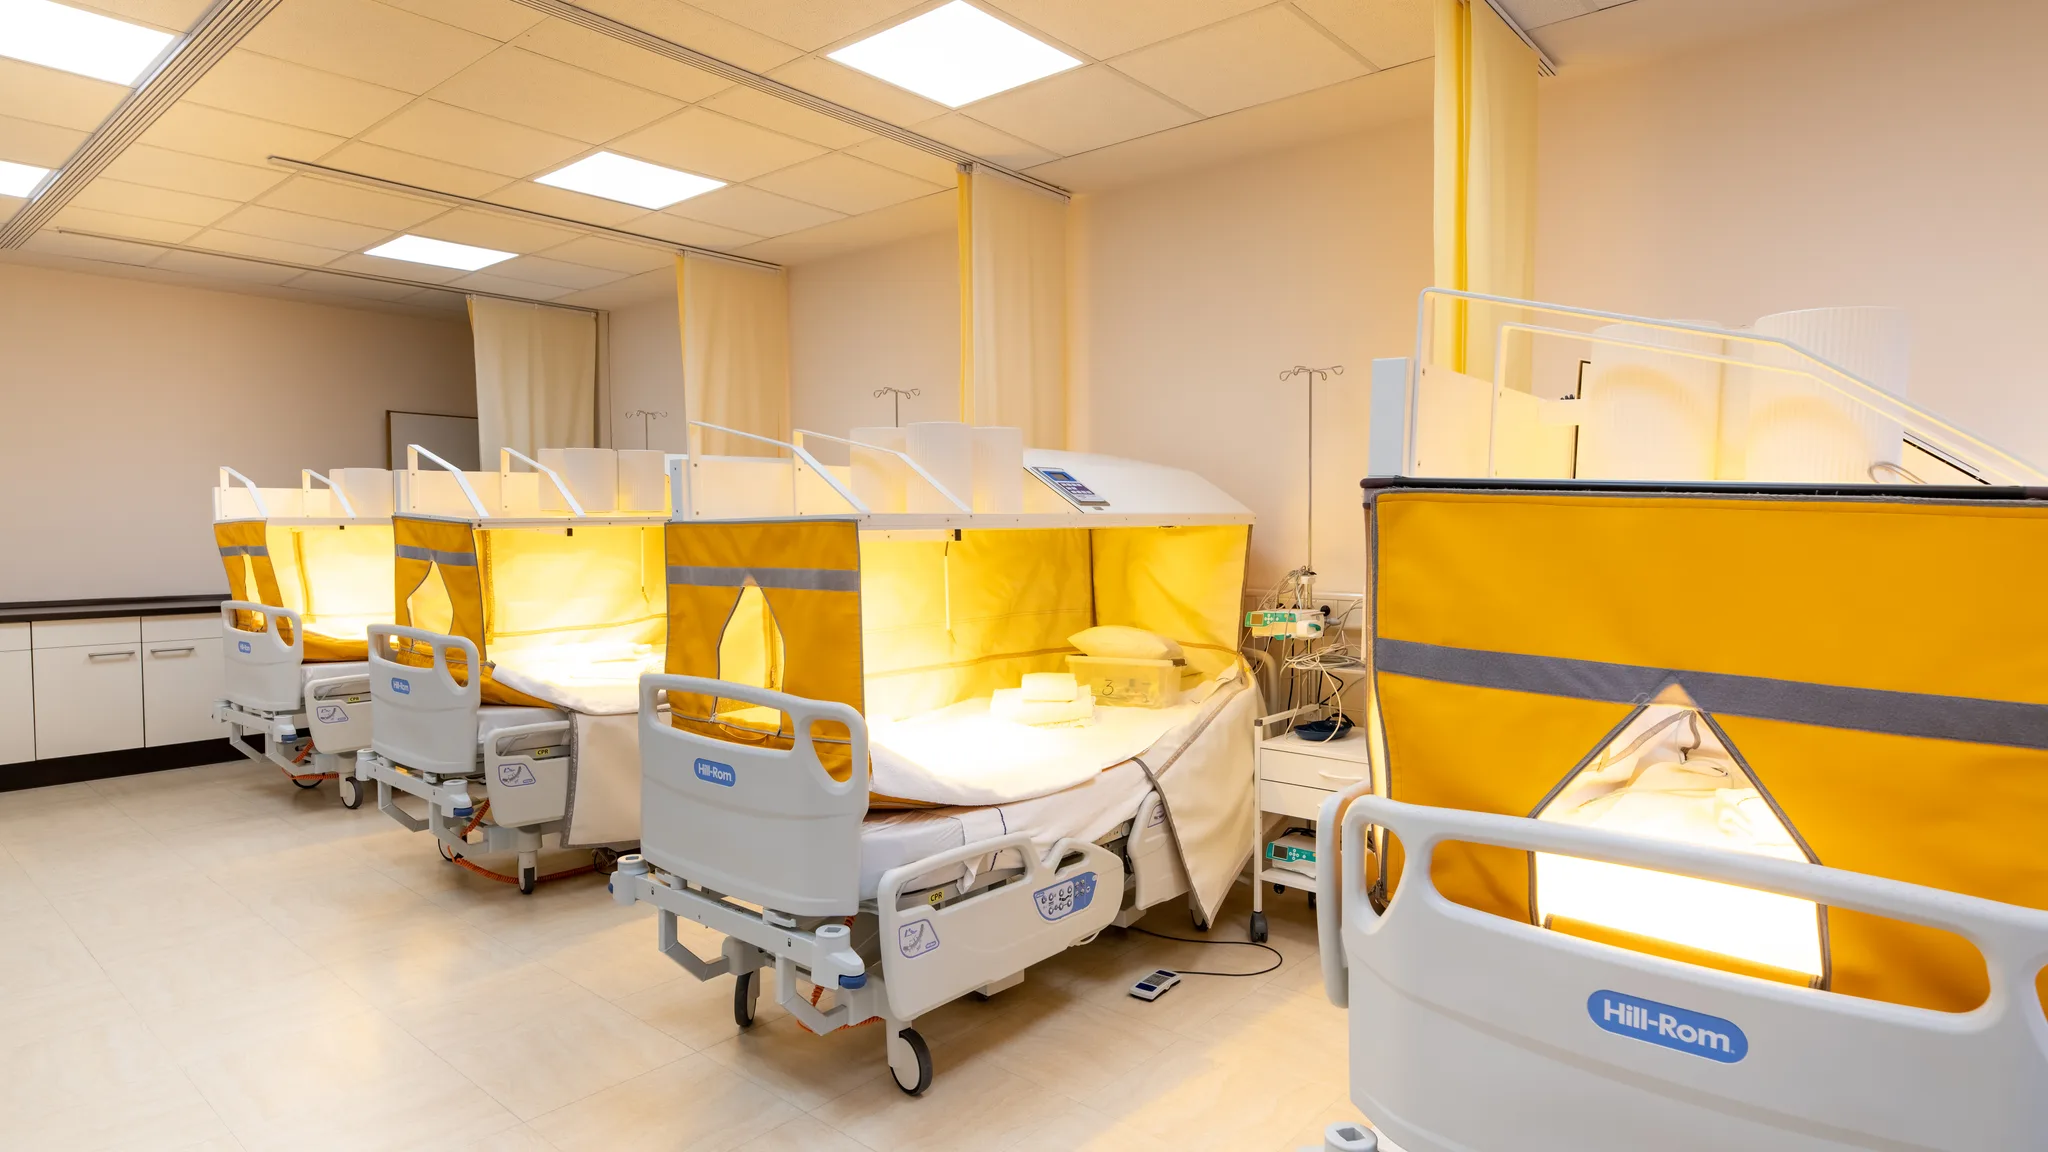
Whole-body hyperthermia (WBH) raises the core body temperature to the level of a strong fever, without an infection, and holds it there for a set time. You lie under a canopy of water-filtered infrared-A lamps; the filter removes the part of the spectrum that would burn the skin, so the warmth reaches the blood near the surface and is carried into the core. It is the form of hyperthermia at St. George Hospital we use most: more than 30,000 sessions on this ward since 1991, and many patients have been helped by it.
Mild WBH (38.5–40 °C / 101.3–104.0 °F) mainly changes how the immune system behaves; moderate WBH (40–42 °C / 104.0–107.6 °F) adds direct heat stress on tumor cells and pathogens. The Lyme protocol aims for at least 41.6 °C / 106.9 °F while the antibiotic runs, because Borrelia loses viability at raised temperatures in laboratory work. We call it antibiotic-augmented thermoeradication (AAT).
One session, five stages
A nurse and a physician stay at the bed throughout.
Preparation
Vital signs, an IV line and a core-temperature probe; sedation for sessions above 41 °C / 105.8 °F, including the Lyme protocol.
Heating
Water-filtered infrared light raises your temperature step by step, like a building fever, while fluids run by infusion.
Monitoring at target
Held at your protocol's target (Lyme: 41.6–41.8 °C / 106.9–107.2 °F) while the antibiotic runs, with every value watched continuously.
Cooling
Brought down step by step until your values settle.
Rest
The evening is for sleep. Sessions are never on consecutive days.
What heat does to Borrelia in the laboratory
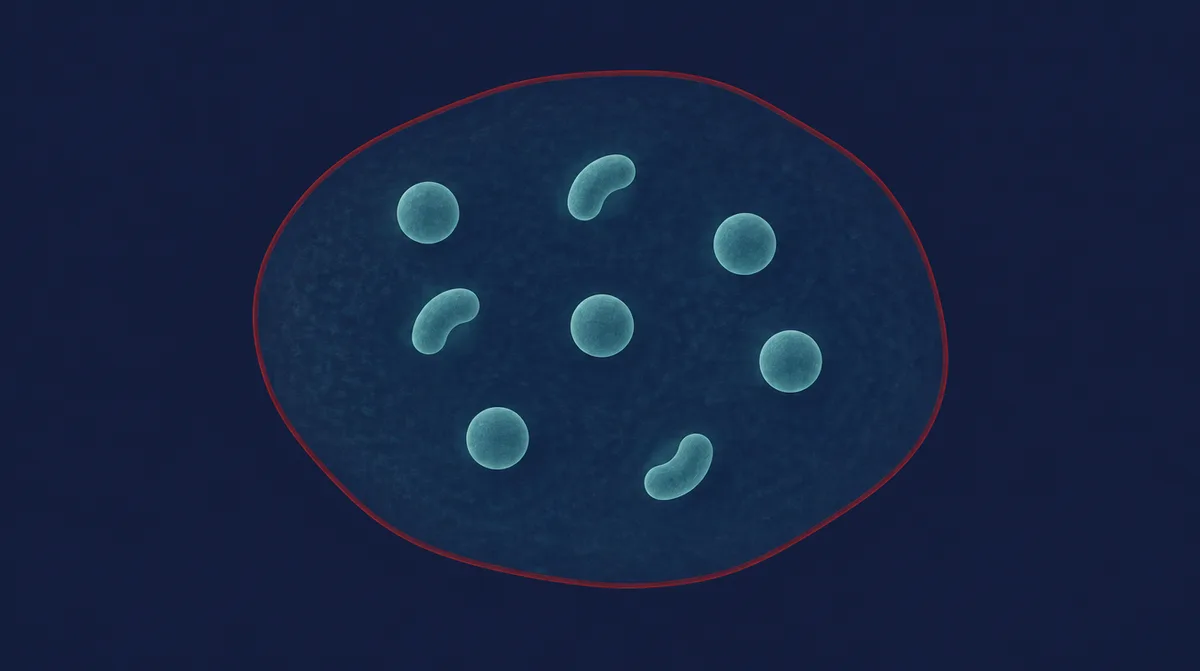
Round-body forms inside a host cell At body temperature, Borrelia can persist in host cells as rounded, dormant forms. 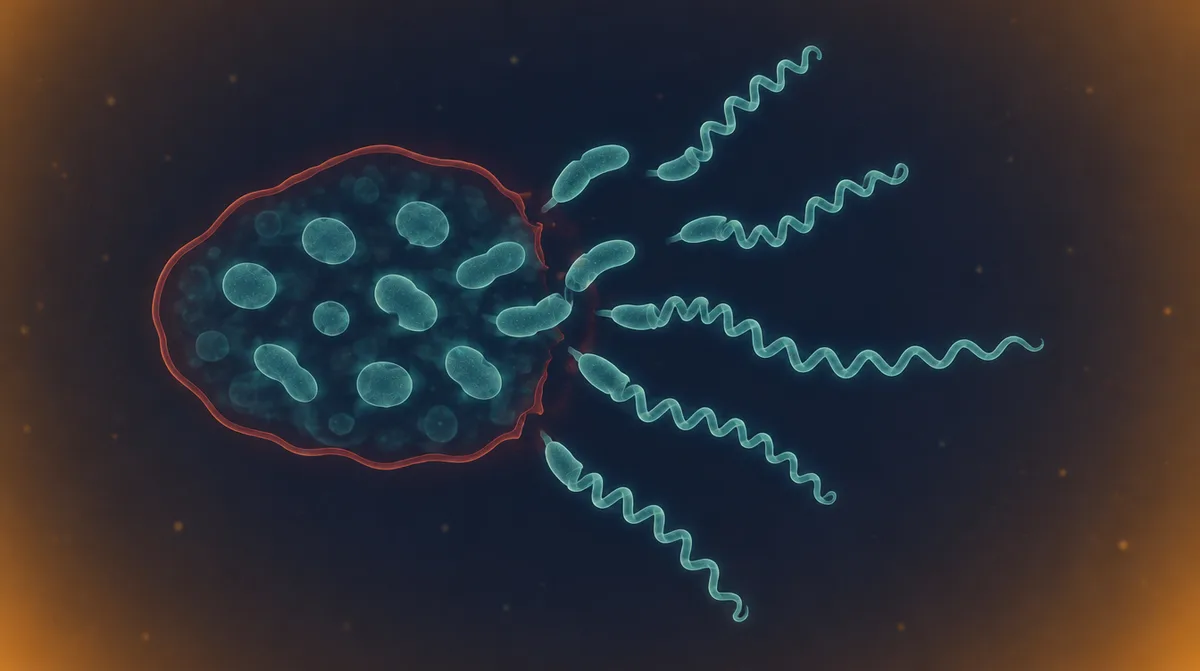
Exit from the cell, spiral form As the temperature rises, the organisms leave the cell and take their spiral form. 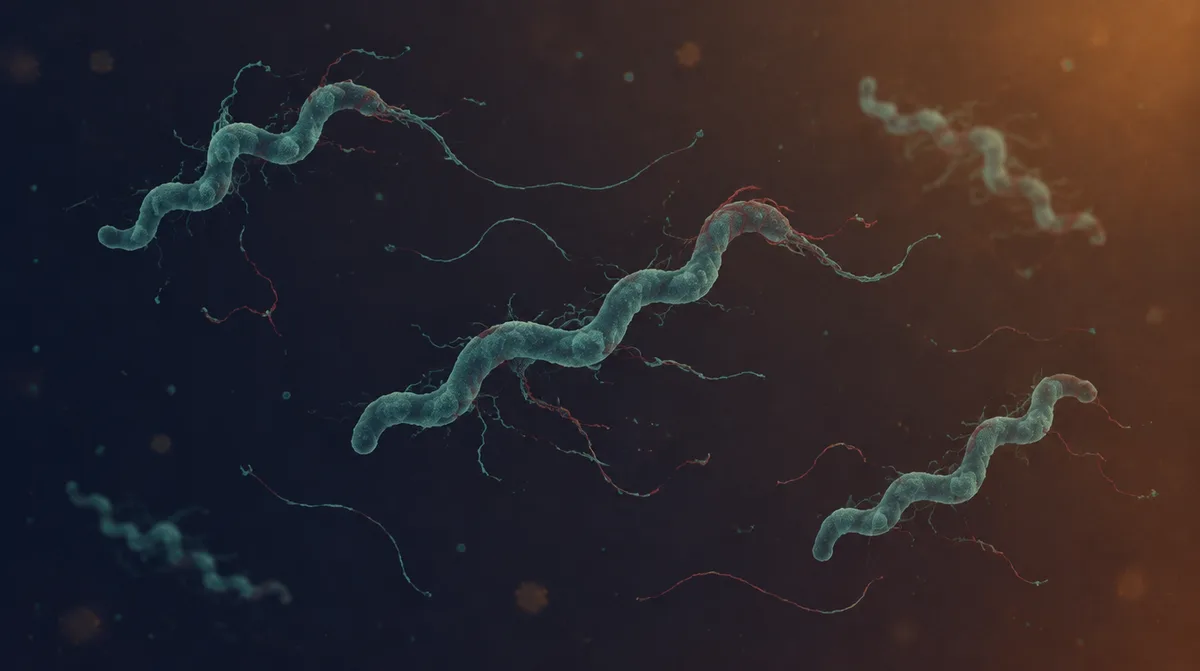
Loss of motility, shedding Under sustained heat stress the spirals lose motility and shed flagellar material. 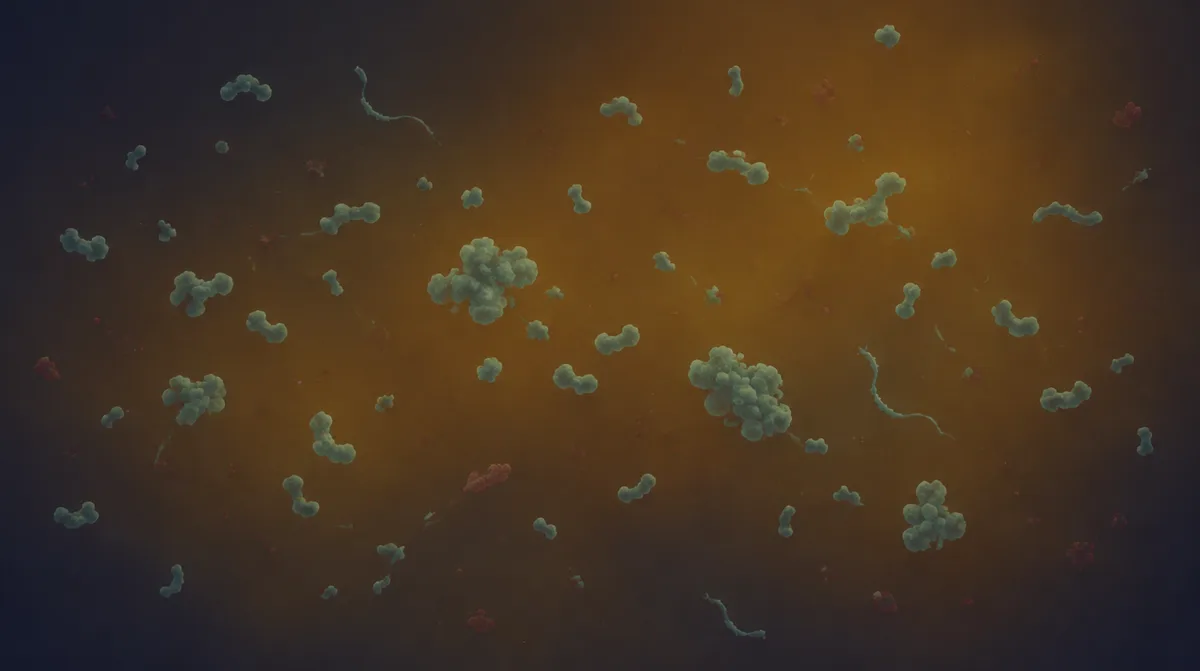
Immobile and fragmented After prolonged exposure the organisms are immobile and fragmented.
Whole-body and local-regional compared
Whole-body
- What it is
- Core temperature raised under water-filtered infrared light
- Used for
- Chronic Lyme disease, integrative oncology; a mild form in ME/CFS and Long COVID
- Session
- 4 to 6 hours, preparation to first rest
- Setting
- Inpatient ward, nurse and physician at the bed; sedation above 41 °C / 105.8 °F
- Recovery after a session
- Very tired that evening, aches possible the next day; in the Lyme program two recovery days follow
Local-regional
- What it is
- A tumor and its surroundings heated to 40–44 °C / 104.0–111.2 °F
- Used for
- Solid tumors, with radiotherapy or chemotherapy
- Session
- About 60 minutes
- Setting
- Treatment room, no anesthesia, nurse nearby
- Recovery after a session
- You go on with your day; skin may stay red for a few hours
Your physician chooses the form from your diagnosis and findings. Both can be part of the same stay, on different days.
What conditions does it treat?
- Chronic Lyme disease and co-infections: the core of the inpatient Lyme program. The two sessions carry the intravenous antibiotics; the days between are for HELP apheresis, ozone therapy and immune infusions (Lyme treatment protocol).
- Cancer, with chemotherapy, immunotherapy or low-dose insulin-potentiated chemotherapy, never in place of the surgery, radiotherapy or chemotherapy your oncologist recommends. Tumor regions can also be treated with local-regional hyperthermia or HFTT.
- Post-COVID syndrome and ME/CFS, in the mild form at 38.5–39.5 °C / 101.3–103.1 °F.
- Chronic inflammatory conditions, decided case by case after the work-up.
Outside standard oncology treatment it is a treatment attempt, decided with you after the screening. For immune activation, fever therapy may be chosen instead.
What a session feels like

Water-filtered infrared-A lamps inside the canopy · Clinicum St. Georg 
A patient room on the ward · Clinicum St. Georg
Like a strong fever: heat, sweating, a fast pulse and thirst. Bring warm clothes for the evening.
Evidence
A randomized trial supports whole-body hyperthermia in major depression; in oncology the evidence comes from smaller studies. In chronic Lyme disease it rests on laboratory data and on decades of our own clinical experience, without controlled trials so far.
Show the studies
In major depression a single session of whole-body hyperthermia was tested against a sham procedure in a randomized clinical trial published in JAMA Psychiatry (Janssen et al., 2016), and a 2019 review asked whether the mood findings are ready for clinical recommendations (Hanusch et al., 2019). That evidence comes from psychiatry and does not cover the conditions treated here; it does show that the procedure can be studied in controlled trials. The history and current uses of the method are reviewed by Vaupel et al., 2022.
In oncology the evidence for whole-body hyperthermia with chemotherapy is limited and comes from smaller studies; the strong hyperthermia evidence in oncology belongs to local-regional hyperthermia with radiotherapy. At fever-range temperatures natural killer cells become more active and cells produce heat shock proteins that mark them for immune recognition (Dayanc et al., 2008).
In chronic Lyme disease the laboratory finding on heat and antibiotics against Borrelia (Reisinger et al., 1996) is the basis of the protocol. The hospital's experience with more than 12,000 Lyme patients since 1995 has not been tested in a controlled trial. We measure before the first session and again in the second week, and what the sessions change for you shows in those measurements and in the follow-up.
Risks and who should not have it
Whole-body hyperthermia is intensive. An ECG and a lung-function test come first, and it is not given in severe heart or vascular disease, uncontrolled seizures, pregnancy, acute thrombosis, severe anemia, active bleeding or brain metastases.
Show contraindications and side effects
Who is excluded
The physicians do not perform whole-body hyperthermia in patients with severe disease of the heart or blood vessels or a recent heart attack, epilepsy or another seizure disorder that is not controlled, pregnancy, acute thrombosis, severe anemia, active bleeding or a clotting disorder, or brain metastases. Where needed, an echocardiogram or stress ECG is added to the screening. The decision is made after the review of your records and the screening, and the treatment is offered only within an inpatient program.
Side effects
The expected effects are those of a strong fever: exhaustion that evening, thirst, a fast pulse, sweating, and muscle aches the next day. Fluid is replaced by infusion during the session. Some Lyme patients have a temporary Herxheimer reaction, a short worsening of symptoms, which the team monitors and treats. Rarer problems, such as a drop in blood pressure or a skin reaction under the heating unit, are the reason a nurse and a physician stay in the room and the monitoring is continuous.
Common questions about whole-body hyperthermia
Is whole-body hyperthermia safe?
It is an intensive procedure, which is why it runs only inside an inpatient program after screening with an ECG and a lung function test. Patients with severe heart or vascular disease, uncontrolled seizures, pregnancy, acute thrombosis, severe anemia, active bleeding or brain metastases are not treated. A nurse and a physician stay at the bed and monitor core temperature, heart rate, oxygen level and blood pressure for the whole session.
Does whole-body hyperthermia hurt?
The only needle is the intravenous line. The session itself feels like a strong fever: heat, sweating, a fast pulse and thirst. Sessions above 41 °C / 105.8 °F, including the Lyme protocol, are performed under sedation, so you sleep through the hottest phase. At lower temperatures you rest or doze. The evening afterwards you will be very tired.
How many sessions will I need?
The core Lyme module includes 2 sessions in 2 weeks, each with intravenous antibiotics. In oncology and in ME/CFS the physician sets the number from your diagnosis and from how you tolerate the first session; the sessions are spread over the program with recovery days between them.
What is the difference between whole-body and local-regional hyperthermia?
Whole-body hyperthermia raises the temperature of the whole body from outside, under infrared light, in a session of 4 to 6 hours including the time at the target temperature and the cooling phase. Local-regional hyperthermia heats one region, for example a tumor and its surroundings, to 40–44 °C / 104.0–111.2 °F for about an hour with a radiofrequency applicator and needs no anesthesia. The hospital uses local-regional hyperthermia mainly in oncology.
How much does whole-body hyperthermia cost?
Whole-body hyperthermia is billed as part of the inpatient program, not per session. After a physician has reviewed your findings, the International Office sends you a written, itemized cost overview: a package price plus individual add-ons. A deposit is paid before admission. The costs and insurance page explains the details.
References
- Whole-Body Hyperthermia for the Treatment of Major Depressive Disorder: A Randomized Clinical Trial. JAMA Psychiatry 2016. PMID 27172277
- The impact of whole-body hyperthermia interventions on mood and depression - are we ready for recommendations for clinical application?. Int J Hyperthermia 2019. PMID 31159624
- Whole-Body Hyperthermia (WBH): Historical Aspects, Current Use, and Future Perspectives 2022. PMID 37494515
- Antibiotics and increased temperature against Borrelia burgdorferi in vitro. Scand J Infect Dis 1996. PMID 8792482
- Dissecting the role of hyperthermia in natural killer cell mediated anti-tumor responses. Int J Hyperthermia 2008. PMID 18214768
Send a free inquiry
The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.
- Phone
- +49 8061 398-0
- Hours
- Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.
Munich Airport (MUC), about 60 minutes by car.