Is this you?

Active surveillance sounds like doing nothing. You are not built for that.

A Gleason score, a PSA graph, and two options that both frightened you: surgery with its risks, or waiting. You want to know whether there is something reasonable to do in the meantime, and whether real monitoring stands behind it.

What it is

How the hospital approaches prostate cancer

Prostate cancer ranges from slow-growing, low-risk tumors that may never cause symptoms to cancers that spread early. Treatment decisions depend on stage, Gleason score, PSA kinetics, age and what you are prepared to accept, and the standard options each carry a cost: prostatectomy and radiotherapy with their risk of incontinence and erectile dysfunction, hormone therapy with its loss of muscle, bone and drive, surveillance with the weight of an untreated diagnosis.

St. George Hospital treats prostate cancer in three settings. Alongside radiotherapy or hormone therapy, immune support and supportive care are coordinated with the treatment your urologist has planned. For men on active surveillance, the hospital offers a monitored program next to the surveillance schedule, as an individual treatment attempt decided with the patient after medical consultation. In biochemical recurrence or metastatic disease, the program runs beside the systemic treatment your oncologist prescribes. Dr. Martin Rößner, Chief Physician for internal medicine and oncology, writes each plan with the ward team. None of the therapies on this page is offered as a replacement for a treatment your urologist or oncologist recommends.

Benign enlargement and prostatitis are treated on a separate page, prostate health, because the aim and the method differ.

A middle-aged man seen from behind on a lakeside bench at a Bavarian lake
How we treat

What the hospital combines for prostate cancer

Whole-body hyperthermia

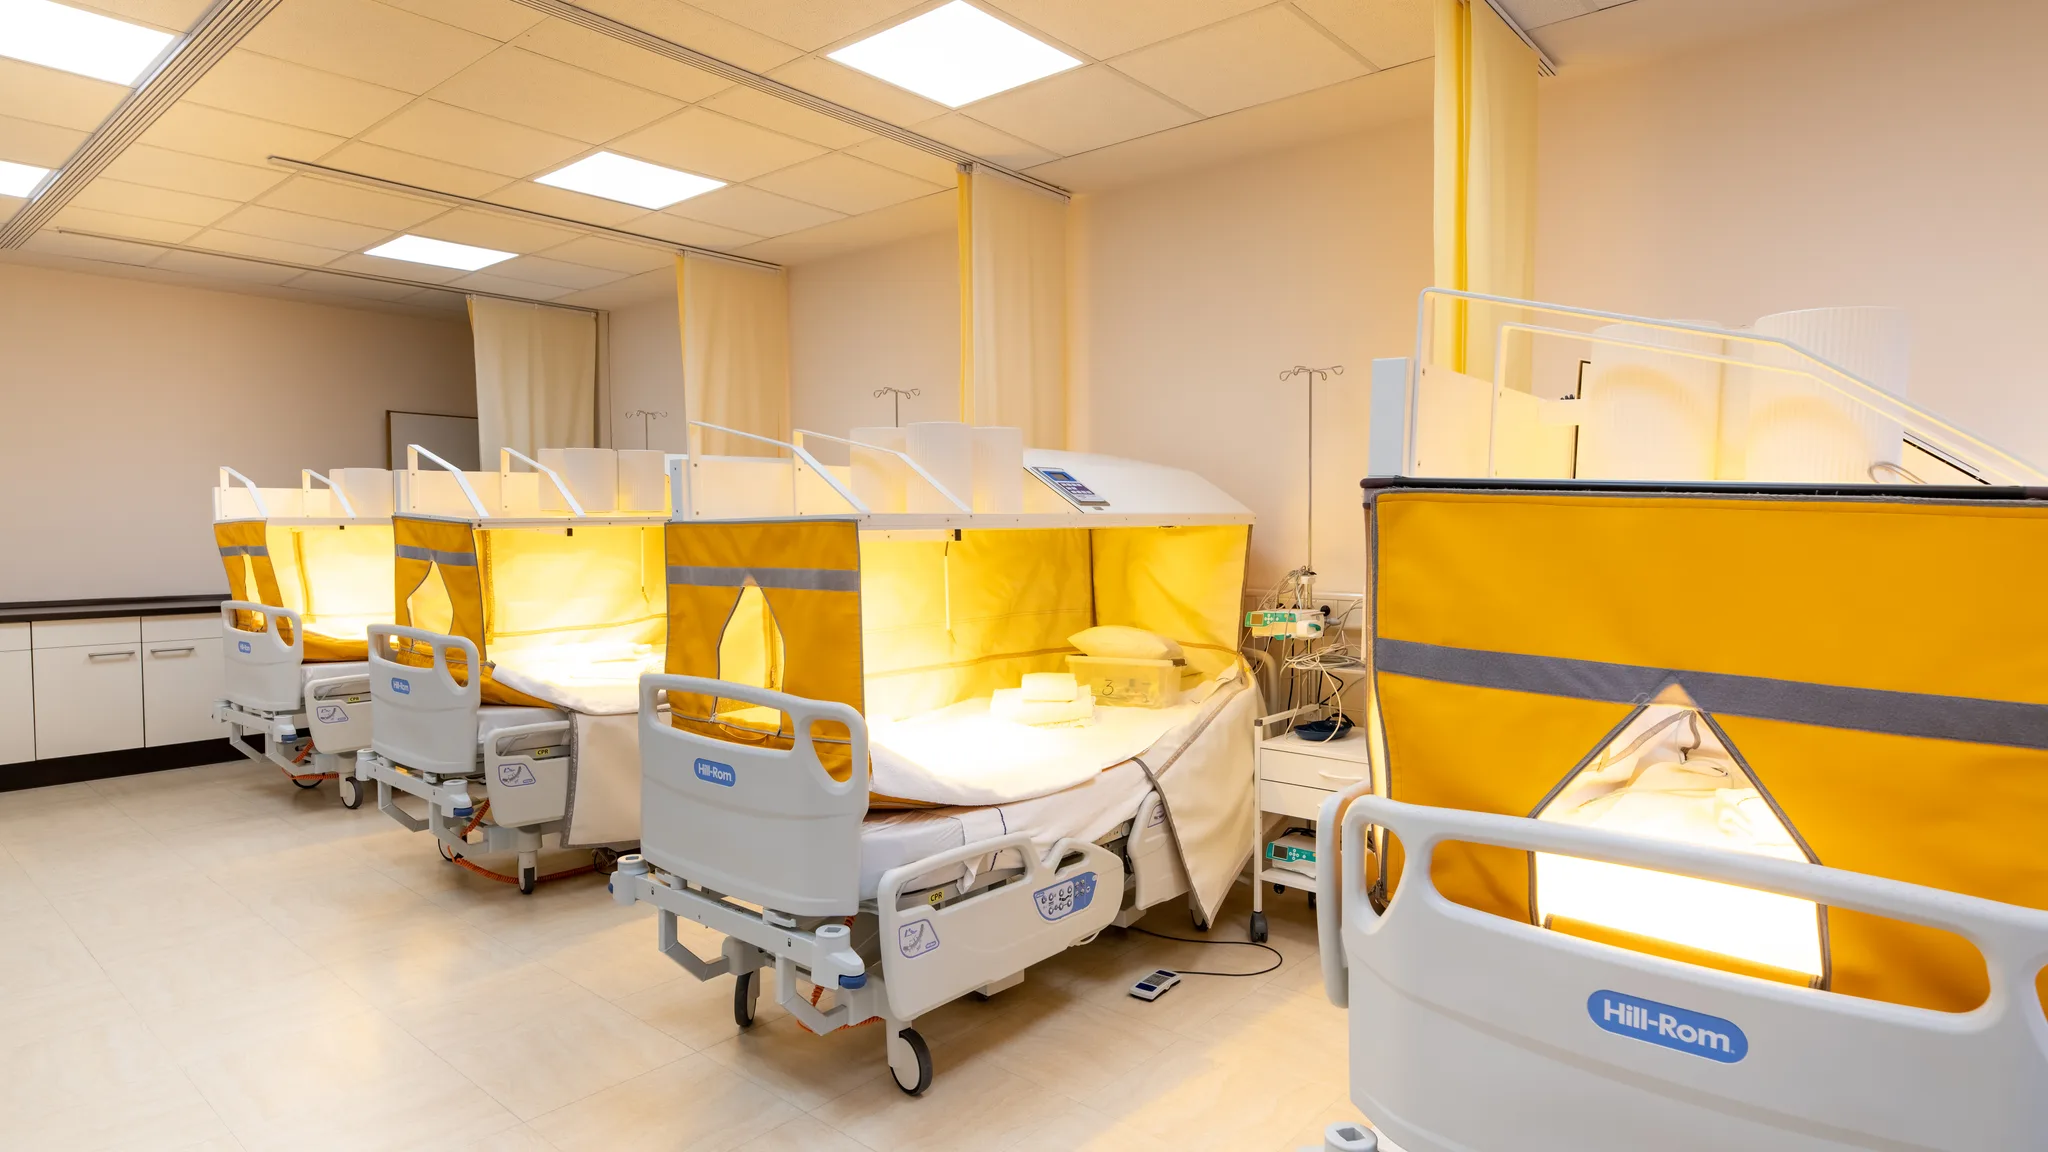
The core temperature is raised under continuous monitoring in a session of four to six hours, with a physician and nurse present. Used in metastatic disease alongside hormone therapy or chemotherapy; the evidence here is emerging, from cohort data.

What a whole-body session involves

Immune therapy

Thymus peptides, mistletoe and, for selected patients, dendritic cell therapy, chosen from the immune profile taken on arrival. Used across all three settings, with the aim of supporting immune function during treatment; the evidence for dendritic cell therapy is emerging.

What immune therapy involves

IPT low-dose chemotherapy

Insulin first, then a fraction of the standard chemotherapy dose, then glucose, with a physician and nurse at the chair. Considered in castration-resistant disease for men who no longer tolerate full-dose chemotherapy, after consultation with the oncologist. The evidence is limited.

How IPT low-dose chemotherapy works

Hormones, nutrition and lifestyle

The hormone therapy your urologist prescribes stays as it is. The hospital measures testosterone, estradiol, DHT and vitamin D, and writes nutrition, supplementation (vitamin D, selenium, modified citrus pectin), exercise and stress-management advice from the results and from your bone density.

Four hospital beds in the whole-body hyperthermia room, each under a yellow infrared canopy lit from within
The whole-body hyperthermia room Clinicum St. Georg
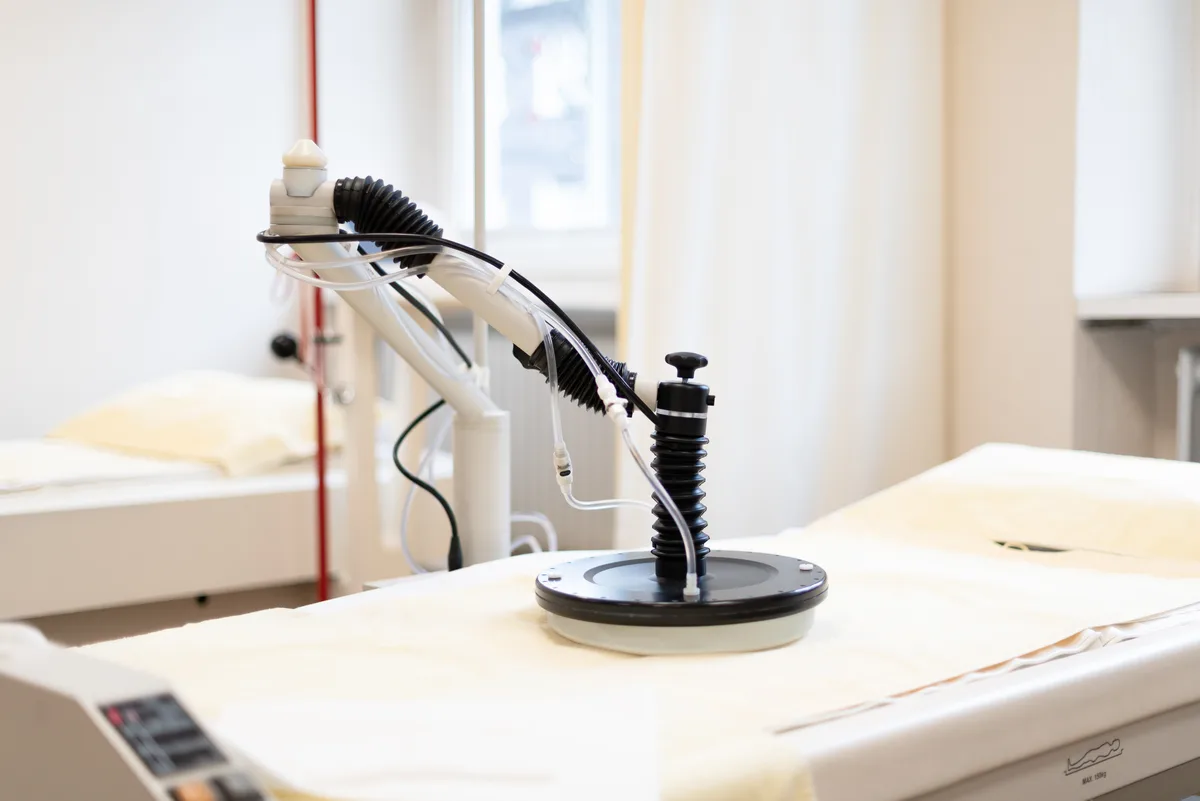
An articulated applicator arm positioned above a treatment couch in a bright room
Local hyperthermia: the applicator is positioned over the treatment area. Clinicum St. Georg
Who this is for

Common patient scenarios, and who is excluded

  • Men with newly diagnosed low- or intermediate-risk disease who have chosen active surveillance and want a monitored program beside it
  • Men in radiotherapy or hormone therapy seeking coordinated immune support and supportive care
  • Men with rising PSA after surgery or radiotherapy (biochemical recurrence), in coordination with the urologist
  • Men with locally extensive disease combining the program with the treatment their urologist has planned
  • Men with metastatic or castration-resistant disease looking for additions to systemic treatment

A performance status that no longer allows a two-week stay, or a disease that calls for immediate surgery or radiotherapy, are the usual reasons the physicians advise against traveling. We tell you this in writing after the records review.

From your records to the follow-up

  1. Before you travel

    After the International Office requests them, the oncology team reads your biopsy report, MRI, PSA history and treatment summary. A video consultation and a written cost overview follow.

  2. First two days

    days 1 to 2

    PSA (total, free and ratio), the hormone panel, immune status and organ function, plus a transrectal ultrasound. The plan is written with you.

  3. During the stay

    Immune support and supportive care according to your written plan, coordinated with your treating oncologist. A physician sees you every day.

  4. Discharge

    A report for your urologist, a supplementation plan and the dates for PSA checks at home. Follow-up questions go to the International Office.

Integrative oncology program in Germany

What the evidence shows for prostate cancer, and what it does not

Standard treatments and active monitoring have clinical trial evidence. Evidence for complementary measures differs by therapy; these do not replace your urologist’s treatment or surveillance plan.

Read the evidence in detail

Evidence is graded on this page in four words: strong, moderate, emerging and limited. The evidence for a standard cancer treatment cannot be transferred to a different complementary therapy.

Standard options: strong. The ProtecT trial randomized 1,643 men with PSA-detected localized prostate cancer to active monitoring, prostatectomy or radiotherapy and followed them for a median of ten years. Deaths from prostate cancer were rare (17 in all) and did not differ significantly between the three groups; metastases and disease progression were more frequent in the monitoring group (Hamdy et al., N Engl J Med, 2016). That is the background against which every addition on this page has to be judged.

Immune therapy: emerging. The approved cellular immunotherapy sipuleucel-T prolonged median survival by about four months in metastatic castration-resistant prostate cancer (Kantoff et al., N Engl J Med, 2010). That product is a different therapy from the dendritic cell therapy given here, and ours has no trial of that kind.


Costs and billing

Treatment at St. George Hospital is self-pay. Costs are individual: a package price plus individual add-ons, set out in a written, itemized cost overview after a physician has read your findings. A deposit is paid before admission. After the stay you receive an itemized invoice in English that you can submit to your insurer; reimbursement is not promised. Details are on costs and insurance.

Traveling here

Patients from more than 60 countries have been treated on the ward. Munich Airport is about 60 minutes by car; the International Office arranges the transfer (charged extra), accommodation for a companion and the video consultation before you travel. The practical side is under information for international patients.

In the room

A story of hope

“We couldn’t have had a more positive experience and we are very hopeful. We made so many friends and met lovely patients from all over the world who touched our hearts with their faith and love.”

International Patient’s Spouse

Prostate Cancer, 2025

FAQ

Questions patients ask about prostate cancer treatment here

Is active surveillance a reasonable choice?

For low-risk, localized disease, yes. The ProtecT trial followed 1,643 men for a median of ten years and found deaths from prostate cancer rare and no significant difference in mortality between monitoring, surgery and radiotherapy, although metastases and progression were more frequent with monitoring. The hospital respects that choice and offers a program alongside it, never instead of it.

Do you treat metastatic or castration-resistant prostate cancer?

Yes, alongside the systemic treatment your oncologist prescribes. The program then centers on whole-body hyperthermia, immune therapy and supportive care, and on tolerance of the hormone therapy or chemotherapy you are receiving. Our dendritic cell therapy is a different product from the one tested in the sipuleucel-T trial, and we do not claim that trial's result for ours.

How much does the program cost?

This page lists no prices. After a physician has reviewed your findings, you receive a written, itemized cost overview: a package price plus individual add-ons. Nothing is booked before you have it. Details are on costs and insurance.

If you want to know whether the program is reasonable for your stage, send your biopsy report, MRI, PSA history and treatment summary. Dr. Rößner's team reads them before the video consultation and answers in writing.

References

  1. 10-Year Outcomes after Monitoring, Surgery, or Radiotherapy for Localized Prostate Cancer.. N Engl J Med 2016. PMID 27626136
  2. Sipuleucel-T immunotherapy for castration-resistant prostate cancer.. N Engl J Med 2010. PMID 20818862

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry