

Is this you?

You did one normal thing yesterday. Today you are paying for it.

A trip to the grocery store, a walk with the dog, a work call that ran long. Twenty-four hours later your legs are lead, your head is cotton, and nobody around you can see why. You have learned to ration yourself like a battery that never fully charges.

The mechanism

What mitochondria do

Every cell in the human body contains hundreds to thousands of mitochondria, the organelles that produce adenosine triphosphate (ATP), the energy currency of the cell. Your body produces and consumes roughly its own weight in ATP every day.

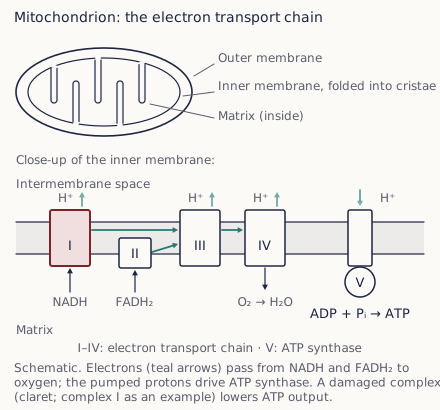
Mitochondria convert nutrients from food and oxygen from breathing into ATP through oxidative phosphorylation. The process runs through five enzyme complexes in the electron transport chain, each of which can be damaged by infection, toxins, oxidative stress or a missing cofactor.

When mitochondria underperform, the organs with the highest energy demand feel it first: the brain, the heart, the muscles and the immune system. That is why the shortfall produces such a wide range of symptoms, from cognitive impairment to exercise intolerance to infections that will not clear.

Gloved hands operating a laboratory blood analyser
Blood diagnostics in the clinic laboratory. Clinicum St. Georg
What the research shows

Is mitochondrial dysfunction real in ME/CFS?

Yes, and it is one of the better replicated findings in the illness. Immune cells taken from ME/CFS patients produce less energy under demand than cells from healthy controls (Tomas et al., 2017), and the impairment tracks with the severity of the illness (Tomas et al., 2020). Metabolomic profiling of the blood describes a hypometabolic state, a cell economy running in a low gear (Naviaux et al., 2016), and a Norwegian group found a pattern pointing to impaired pyruvate dehydrogenase, the enzyme that feeds the mitochondria their main fuel (Fluge et al., 2016). T cells from patients show altered metabolism as well (Mandarano et al., 2020), and the metabolic response to exertion differs from that of healthy people, which is one explanation for post-exertional malaise (McGregor et al., 2019). A 2025 review sets the findings in order (Syed et al., 2025); the same mechanisms are now described in Long COVID (Molnar et al., 2024).

The evidence that mitochondria are involved is moderate and consistent. What it does not show is a single mitochondrial defect that explains every patient, or a blood test that diagnoses ME/CFS on its own. The findings sit next to immune, autonomic and vascular changes in the same patients, which is why the work-up on the diagnosis page looks at all of them.

Mechanisms of Failure

What damages mitochondria?

Viral infections

Viruses including SARS-CoV-2, EBV and HHV-6 can damage mitochondrial membranes, use the mitochondrial machinery for their own replication, and trigger the cell's self-destruction pathways. Post-infectious mitochondrial damage is a shared mechanism of Long COVID and ME/CFS.

Oxidative stress

Stressed mitochondria produce excess reactive oxygen species that damage their own membranes, DNA and enzyme complexes. The cycle feeds itself: damaged mitochondria produce more oxidants, which damage more mitochondria.

Nutrient deficiency

The electron transport chain needs specific cofactors: CoQ10, NAD+, riboflavin (B2), niacin (B3), iron, magnesium and others. A shortfall in any of them creates a bottleneck in energy production. Many ME/CFS patients show several subclinical deficiencies at once.

Toxic exposure

Heavy metals (mercury, lead, aluminum), pesticides, mycotoxins and certain medications (statins, fluoroquinolone antibiotics) are known mitochondrial toxins. Environmental exposure is an under-recognized contributor and is part of the history we take.

Chronic inflammation

Pro-inflammatory cytokines (TNF-alpha, IL-1, IL-6) impair mitochondrial function directly. Chronic low-grade inflammation from any source, a persistent infection, a leaky gut, an autoimmune process, erodes the mitochondria's ability to produce energy.

Hormonal imbalance

Thyroid hormones regulate the production of new mitochondria. Cortisol dysregulation impairs cellular energy metabolism, and sex hormones influence mitochondrial efficiency. An imbalance compounds the energy deficit, which is why the hormones are in the work-up.

Diagram of a mitochondrion with the electron transport chain
Mitochondrion: the electron transport chain. Schematic, not to scale.
What we test

How we assess mitochondrial function

Standard laboratory tests do not evaluate mitochondrial health. At St. George Hospital the functional medicine work-up maps the specific nature of each patient's impairment in the first days of the stay:

  • ATP profile: measures the ATP production capacity, the recycling efficiency, and which mitochondrial complexes are impaired
  • Organic acid testing: urinary organic acids reveal metabolic blocks in the citric acid cycle and the electron transport chain
  • Oxidative stress panel: lipid peroxidation, 8-OHdG as a marker of DNA damage, and antioxidant capacity
  • CoQ10, NAD+ and cofactor levels: direct measurement of the essential mitochondrial cofactors
  • Lactate to pyruvate ratio: a raised ratio indicates a shift from aerobic to anaerobic metabolism
  • Intracellular mineral and vitamin analysis: red blood cell mineral levels and functional vitamin testing

The same values are measured again in the second week of the program. That repeat measurement is how we know whether the treatment is doing what it was chosen to do.

Abstract teal and navy visual
Treatment

Mitochondrial repair therapy

The mitochondrial protocol aims to restore ATP production, reduce oxidative damage and rebuild mitochondrial capacity. It is written from your test results and adjusted to the repeat measurements, as one part of the ME/CFS treatment program.

IV micronutrient therapy

Intravenous delivery of CoQ10, NAD+, alpha-lipoic acid, B-complex vitamins, magnesium and glutathione bypasses absorption problems and reaches intracellular concentrations that oral supplements alone do not. What goes into the infusion follows the cofactor levels on your work-up.

Detoxification

Removal of mitochondrial toxins such as heavy metals, mycotoxins and environmental pollutants through targeted chelation, liver support and, where the findings call for it, apheresis, takes away an ongoing source of damage.

Antioxidant support

Breaking the oxidative stress cycle with IV glutathione, vitamin C and targeted antioxidant therapy protects the mitochondria you have and creates the conditions for new ones to form.

Oral maintenance protocol

After the intensive IV phase you continue with an oral protocol, CoQ10, PQQ, D-ribose, acetyl-L-carnitine and B vitamins, to hold and build on what the inpatient weeks achieved. The letter to your home physician lists it.

How strong is the evidence for these treatments? Small randomized trials of oral CoQ10 plus NADH in ME/CFS reported effects on fatigue perception and on biochemical markers (Castro-Marrero et al., 2015), and a systematic review of nutrition interventions in the illness grades the evidence overall as limited (Campagnolo et al., 2017). For hyperbaric oxygen in ME/CFS there is a small clinical study (Akarsu et al., 2013); for intermittent hypoxia-hyperoxia training the controlled trials come from other patient groups (Bayer et al., 2017). We say so plainly: the mitochondrial protocol is an individual treatment attempt, decided with you after medical consultation, and its effect is read in the repeat measurements rather than assumed. For international patients it runs inside the Long COVID and ME/CFS apheresis program, a two to three week inpatient stay with a video consultation in English before you travel.

Related Conditions

Mitochondrial dysfunction also affects

  • About the conditionPost-COVID syndrome

    SARS-CoV-2 damages mitochondria, which contributes to the fatigue and brain fog of Long COVID.

  • About the conditionLyme disease

    Borrelia and co-infections impair mitochondrial function and drive the fatigue of chronic Lyme.

  • About the conditionLongevity & aging

    Mitochondrial decline is a hallmark of aging. Supporting mitochondrial health is central to longevity medicine.

FREQUENTLY ASKED QUESTIONS

Common questions about mitochondrial dysfunction

Is mitochondrial dysfunction the cause of ME/CFS?

It is one of the best replicated findings, not the whole explanation. Immune cells from ME/CFS patients produce less energy on demand, and the blood shows a hypometabolic pattern, but these changes sit next to immune, autonomic and vascular findings in the same patients. We treat the mitochondrial part because it is measurable and because it responds to what we can give.

Can mitochondrial dysfunction be measured with a normal blood test?

No. Standard panels do not look at energy production. At St. George Hospital the work-up uses an ATP profile, urinary organic acids, an oxidative stress panel, the lactate to pyruvate ratio and cofactor levels such as CoQ10 and NAD+. The same tests are repeated after treatment, so you see whether the values moved.

Do CoQ10 and NAD+ supplements work in ME/CFS?

Small randomized trials of oral CoQ10 plus NADH reported effects on fatigue perception and biochemical markers, and a systematic review of nutrition interventions grades the evidence as limited. That is why we measure your cofactor levels first and give what is low, intravenously during the stay and orally afterwards, rather than prescribing a standard list.

Is treatment for mitochondrial dysfunction part of the inpatient program?

Yes. The mitochondrial work-up and the IV protocol that follows it are part of the Long COVID and ME/CFS program, a two to three week inpatient stay. Therapies such as IHHT and NAD+ infusions are scheduled from the findings, and the markers are repeated in the second week.

Is mitochondrial dysfunction reversible?

Mitochondria are renewed throughout life, which is the basis of treatment. What the program can do for you shows in the repeat measurements: ATP production, the lactate to pyruvate ratio and the oxidative stress markers after the course, next to how your days feel. We discuss what is realistic for your history in the first consultation.

Related therapies

Treatments for mitochondrial support

  • TherapyIHHT oxygen therapy

    Intermittent hypoxia-hyperoxia training is used to stimulate the formation of new mitochondria and the removal of damaged ones through controlled changes in oxygen.

  • TherapyNAD+ IV therapy

    NAD+ is needed by the electron transport chain.

  • TherapyHyperbaric oxygen (HBOT)

    Pressurized oxygen raises the oxygen available to the tissues for cellular respiration during and after the session.

  • TherapyOzone therapy

    Medical ozone therapy is used to improve oxygen utilization at the cellular level and to lower the oxidative stress that damages mitochondria.

References

  1. Cellular bioenergetics is impaired in patients with chronic fatigue syndrome. PLoS One 2017. PMID 29065167
  2. The effect of myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) severity on cellular bioenergetic function. PLoS One 2020. PMID 32275686
  3. Metabolic features of chronic fatigue syndrome. Proc Natl Acad Sci U S A 2016. PMID 27573827
  4. Metabolic profiling indicates impaired pyruvate dehydrogenase function in myalgic encephalopathy/chronic fatigue syndrome. JCI Insight 2016. PMID 28018972
  5. Mitochondrial Dysfunction in Myalgic Encephalomyelitis/Chronic Fatigue Syndrome. Physiology (Bethesda) 2025. PMID 39960432
  6. Post-Exertional Malaise Is Associated with Hypermetabolism, Hypoacetylation and Purine Metabolism Deregulation in ME/CFS Cases. Diagnostics (Basel) 2019. PMID 31277442
  7. Myalgic encephalomyelitis/chronic fatigue syndrome patients exhibit altered T cell metabolism and cytokine associations. J Clin Invest 2020. PMID 31830003
  8. Mitochondrial dysfunction in long COVID: mechanisms, consequences, and potential therapeutic approaches. Geroscience 2024. PMID 38668888
  9. Does oral coenzyme Q10 plus NADH supplementation improve fatigue and biochemical parameters in chronic fatigue syndrome?. Antioxid Redox Signal 2015. PMID 25386668
  10. Dietary and nutrition interventions for the therapeutic treatment of chronic fatigue syndrome/myalgic encephalomyelitis: a systematic review. J Hum Nutr Diet 2017. PMID 28111818
  11. The efficacy of hyperbaric oxygen therapy in the management of chronic fatigue syndrome. Undersea Hyperb Med 2013. PMID 23682549
  12. Intermittent hypoxic-hyperoxic training on cognitive performance in geriatric patients. Alzheimers Dement (N Y) 2017. PMID 29067323

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry