



Gloved hands operating a laboratory blood analyser

Post-COVID Diagnostics

Diagnostic work-up for post-COVID syndrome

The work-up identifies which mechanisms drive your Long COVID symptoms: microclots, impaired microcirculation, endothelial damage, immune activation, viral remnants, autonomic dysfunction and mitochondrial impairment. It takes one to two days at the start of the stay, and every value in it is measured again later, so the treatment can be judged by numbers.

Is this you?

Your bloodwork is "unremarkable." Your life is not.

You had COVID, and eighteen months later you still cannot climb the stairs without your heart racing. Your primary care doctor ordered the standard panel and found nothing. The Long COVID clinic has a waitlist longer than your patience.

This page lists what the Long COVID program at St. George Hospital measures, why those tests, and what the results decide.

Why Standard Tests Miss Post-COVID

Is there a test for long COVID?

No single test diagnoses Long COVID. The diagnosis rests on the history and on excluding other causes; what a work-up can do is show which mechanisms are active in you. The frustration of "normal" results from conventional blood work while symptoms continue is not a sign that the symptoms are imaginary. Standard panels were not designed to detect the processes that drive post-COVID syndrome.

Those processes have been described in the research literature: fibrin amyloid microclots that resist the body's clot-dissolving enzymes (Pretorius et al., 2021), endothelial dysfunction with altered endothelial biomarkers (Haffke et al., 2022), a persistent loss of capillaries in the skin (Osiaevi et al., 2023), circulating spike protein months after infection (Swank et al., 2023), reactivated Epstein-Barr virus (Rohrhofer et al., 2023), functional autoantibodies (Wallukat et al., 2021) and autonomic disorders such as POTS (Blitshteyn et al., 2021). None of them shows on a routine blood count or metabolic panel.

The post-COVID work-up at St. George Hospital is built to measure these mechanisms. Impaired microcirculation, microclots and endothelial dysfunction are the research direction we work on with Dr. Beate Jaeger, and the symptoms and causes page explains how each mechanism produces the symptoms you feel.

Abstract teal and navy visual
Post-COVID recovery treatment at St. George Hospital Germany
Microvascular Research

Microcirculation and microclots: what we measure and why

Dr. Beate Jaeger, Chief Physician for internal and laboratory medicine, studies microvascular dysfunction in post-COVID syndrome. The working model is that impaired microcirculation, often invisible to conventional imaging, underlies persistent fatigue, cognitive dysfunction, exercise intolerance and organ-level symptoms in Long COVID.

Microclots, or fibrin amyloid microclots, are abnormal clot structures in the smallest vessels that resist normal fibrinolysis. They impair the delivery of oxygen and nutrients to the tissues, which fits the multi-organ symptoms of Long COVID; a 2022 study described their prevalence next to symptoms and platelet pathology in a Long COVID cohort (Pretorius et al., 2022).

What the hospital does with this model is measure: the microclot burden under fluorescence microscopy, the microcirculation by capillaroscopy and perfusion measurement, and standardized symptom scores, each before treatment and again during and after it. Whether and how far these values move in a given patient is read from the repeat measurement, not assumed. The diagnostic value of the microclot and microcirculation methods is still an open scientific question, and they are used next to established laboratory tests, not instead of them.

Our Diagnostic Panel

Post-COVID diagnostic workup at St. George

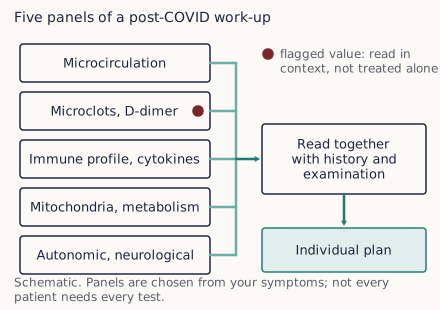
The post-COVID evaluation covers six domains to identify the mechanisms driving your symptoms. Each test category produces a value that informs treatment selection and is measured again to follow the course.

Microcirculation testing

Functional microcirculation assessment using capillaroscopy and perfusion measurement to evaluate the smallest blood vessels. This shows impaired microvascular flow that conventional vascular imaging does not detect and matters for exercise intolerance and organ-specific symptoms.
Microclot detection

Fluorescence microscopy and coagulation analysis to identify fibrin amyloid microclots that persist in the blood of many Long COVID patients. We assess D-dimer, fibrinogen degradation products and platelet activation markers alongside direct microclot visualization to quantify the clot burden and guide apheresis and anticoagulant decisions.

Immune profiling

Immune panel including lymphocyte subsets (CD4, CD8, NK cells), T-cell activation markers, cytokine profiles (IL-6, TNF-alpha, IL-1beta, IL-10), autoantibody screening and complement activation. This shows whether persistent immune activation, immune exhaustion or autoimmune mechanisms are contributing to symptoms, and whether immunoadsorption is worth discussing.

Mitochondrial & metabolic assessment

Mitochondrial function through organic acid testing, lactate to pyruvate ratios, CoQ10 levels and oxidative stress markers (glutathione, MDA, 8-OHdG), plus NAD+ status and B-vitamin levels. Mitochondrial impairment is a described mechanism of Long COVID fatigue (Molnar et al., 2024); the mitochondrial page explains the tests.

Neurological & autonomic

Autonomic function (heart rate variability, tilt-table testing where indicated), neurocognitive screening and neuroinflammatory markers. Many Long COVID patients have dysautonomia, brain fog and cognitive impairment linked to neuroinflammation and microvascular dysfunction in the central nervous system. Where post-exertional malaise leads, a two-day cardiopulmonary exercise test can document it (Gattoni et al., 2025), and is used only when you can tolerate it.

Endothelial & vascular function

Endothelial function testing, von Willebrand factor, ADAMTS13, soluble thrombomodulin and vascular inflammation markers. Endothelial damage is a hallmark of COVID-19 and persists in many Long COVID patients, driving both microvascular and larger-vessel dysfunction. Viral persistence markers (spike and nucleocapsid antibody dynamics, viral RNA in blood and stool) are added where the history points to them.

Diagram of five diagnostic panels for post-COVID assessment: microcirculation, microclots and D-dimer, immune profile and cytokines, mitochondria and metabolism, autonomic and neurological testing, linked by a path
Five panels of a post-COVID work-up. Schematic, not to scale.
The first days

What to expect

The post-COVID work-up is completed over one to two days at the start of the stay, so that the treatment plan can be written early and the treatment weeks used in full. After your first message the International Office requests the records you have before the video consultation: discharge letters, laboratory results, imaging reports, your medication list and a short timeline. Incomplete records are fine; once the International Office has requested them, a physician reads them before the call and tells you which tests are still needed.

For patients from abroad the work-up is the first step of the Long COVID and ME/CFS apheresis program, a two to three week inpatient stay with a video consultation in English before you travel. The ME/CFS diagnosis page describes how the criteria for ME/CFS are applied when the picture points that way.

1

Medical History & Symptom Assessment

Review of your COVID history, symptom timeline, prior treatments and current functional status. Standardized symptom scores record the severity and are repeated later to follow the course.

2

Laboratory Panel

Blood draw on the first morning for the full panel: microcirculation markers, immune profiling, coagulation analysis, metabolic assessment and inflammatory markers.

3

Functional Testing

Microcirculation assessment, autonomic function testing and any organ-specific evaluation your symptom profile calls for, spread over the day with rest between them.

4

Results Conference

Review of all findings with your treating physician. We explain which mechanisms are active in your case and how they connect to your symptoms.

5

Individual Treatment Plan

From the results, a written protocol that names the mechanisms it targets, the therapies chosen, and which values will be measured again, and when.

FREQUENTLY ASKED QUESTIONS

Common questions about post-COVID diagnostics

Is there a test for long COVID?

No single test diagnoses it. Long COVID is diagnosed from the history and by excluding other causes; the work-up then shows which mechanisms are active. Microclot microscopy, endothelial markers, capillaroscopy, autoantibody panels, viral reactivation tests, autonomic testing and mitochondrial markers each measure one part of the picture, and together they decide the treatment plan.

Which records should I send before the video consultation?

Whatever you have: discharge letters, laboratory results, imaging reports, a list of your medication and a short timeline of your illness. Incomplete records are fine. A physician reads them before the call and tells you which tests are still needed and whether the program fits your situation.

How long does the work-up take?

One to two days at the start of the stay. Blood is drawn on the first morning; the functional tests follow over the next day. The results conference with your physician takes place as soon as the laboratory values are in, and the treatment plan is written from it.

Can I have the diagnostics without the treatment program?

The work-up is designed as the first step of the inpatient program, and most patients from abroad combine the two. Whether a diagnostics-only stay is useful in your case is a question for the video consultation; a physician answers it from your records.

Are the microclot and microcirculation tests standard?

Not yet. Microclot detection by fluorescence microscopy and the capillaroscopy of the microcirculation are research-based methods that St. George Hospital uses in its work-up; their diagnostic value is an open scientific question. They are used here next to established laboratory tests, not instead of them.

Related Pages

Continue exploring post-COVID care

Post-COVID program overview

Overview of the post-COVID treatment program: symptoms, causes and how the hospital combines its therapies.

Post-COVID treatment

The treatment protocol in detail: apheresis, immune modulation, oxygen therapies and paced rehabilitation.

Chronic fatigue syndrome

Post-COVID fatigue shares mechanisms with ME/CFS. How the hospital diagnoses and treats persistent fatigue.

Related therapies

Treatments guided by our diagnostics

H.E.L.P. apheresis

When the work-up shows microclots and raised inflammatory proteins, apheresis filters them from the plasma; an individual treatment attempt with emerging evidence.

What H.E.L.P. apheresis involves →

References

  1. Persistent clotting protein pathology in Long COVID/Post-Acute Sequelae of COVID-19 (PASC) is accompanied by increased levels of antiplasmin. Cardiovasc Diabetol 2021. PMID 34425843
  2. Prevalence of symptoms, comorbidities, fibrin amyloid microclots and platelet pathology in individuals with Long COVID/Post-Acute Sequelae of COVID-19 (PASC). Cardiovasc Diabetol 2022. PMID 35933347
  3. Endothelial dysfunction and altered endothelial biomarkers in patients with post-COVID-19 syndrome and chronic fatigue syndrome (ME/CFS). J Transl Med 2022. PMID 35317812
  4. Persistent capillary rarefication in long COVID syndrome. Angiogenesis 2023. PMID 35951203
  5. Persistent Circulating Severe Acute Respiratory Syndrome Coronavirus 2 Spike Is Associated With Post-acute Coronavirus Disease 2019 Sequelae. Clin Infect Dis 2023. PMID 36052466
  6. Association between Epstein-Barr-Virus reactivation and development of Long-COVID fatigue. Biomolecules 2023. PMID 35950630
  7. Functional autoantibodies against G-protein coupled receptors in patients with persistent Long-COVID-19 symptoms. J Transl Autoimmun 2021. PMID 33880442
  8. Postural orthostatic tachycardia syndrome (POTS) and other autonomic disorders after COVID-19 infection. Immunol Res 2021. PMID 33786700
  9. Two-day cardiopulmonary exercise testing in long COVID post-exertional malaise diagnosis. Respir Physiol Neurobiol 2025. PMID 39490617
  10. Mitochondrial dysfunction in long COVID: mechanisms, consequences, and potential therapeutic approaches. Geroscience 2024. PMID 38668888

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry