


Is this you?

Your Lyme test was negative. Your symptoms did not get the memo.

You remember the bite, or you do not. You remember the summer everything changed. Since then: a rheumatologist, a neurologist, a psychiatrist, and a two-tier test that came back negative twice. In a drawer at home is a folder of results that do not add up to anything.

When to seek testing

Symptoms that warrant a full Lyme work-up

Many patients who come to us have been symptomatic for months or years without a clear diagnosis. If you have a combination of the following symptoms, especially if they began after a known or possible tick exposure, a full Lyme work-up should be considered:

  • Persistent fatigue unresponsive to standard treatment
  • Migratory joint or muscle pain without clear orthopedic cause
  • Cognitive impairment, brain fog, or memory difficulties
  • Neurological symptoms: tingling, numbness, nerve pain
  • Cardiac symptoms: palpitations, chest tightness
  • Psychiatric symptoms that appeared suddenly or worsened
  • Symptoms that wax and wane on a cyclical pattern
  • Multiple diagnoses without clear resolution (fibromyalgia, CFS, MS, etc.)
Gloved hands operating a laboratory blood analyser
Blood diagnostics in the clinic laboratory. Clinicum St. Georg
A gloved hand holding a blood sample tube in a laboratory
A blood sample in the clinic laboratory Clinicum St. Georg
Why tests miss it

Why was my Lyme test negative?

Because the two-tier test measures antibodies, not bacteria. A systematic review of North American studies found that its accuracy differs by stage of disease (Waddell et al., 2016): antibody levels can be low early in infection, after early antibiotics, or when the immune response is suppressed. The 2020 IDSA, AAN and ACR guideline itself describes Lyme disease as a diagnosis made from exposure, clinical findings and laboratory support together (Lantos et al., 2021).

The two-tier problem

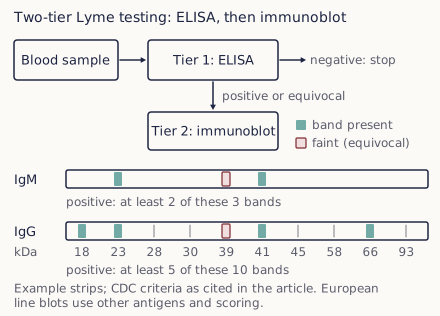
The standard protocol requires a positive ELISA screening test before a Western blot is performed, and the blot needs a set number of reactive bands. A patient whose antibody response is partial, late or suppressed can fail either step and receive a negative result while still infected.

Several factors contribute:

  • ELISA measures antibody levels that may decline in chronic infection
  • Western Blot requires a specific number of reactive bands, excluding patients with partial responses
  • Immune suppression from chronic Borrelia infection reduces antibody production
  • Some Borrelia strains produce antibodies not detected by standard test kits
  • Early antibiotic treatment can prevent full seroconversion

Clinical consequences

Patients with a persisting infection are told they do not have Lyme disease. They receive other diagnoses, symptom-management medication, and often the sentence that their symptoms are psychological.

What follows from a missed diagnosis:

  • Years without treatment of the infection
  • Treatment aimed at the wrong diagnosis
  • Neurological, cardiac and joint involvement that is not recognized as such
  • Co-infections that are never tested for, although ticks frequently carry more than one pathogen (Sanchez-Vicente et al., 2019)

At St. George Hospital no patient is dismissed because of a test limitation. The clinical evaluation always accompanies the laboratory results, and a negative result from home is read, not discarded.

Diagram of two-tier Lyme testing: an ELISA first, and an immunoblot only after a positive or equivocal ELISA
Two-tier testing measures antibodies, not the organism; a negative ELISA stops the sequence. Schematic.
What we test

How we diagnose chronic Lyme disease

The work-up combines the clinical evaluation with laboratory testing in the hospital's own laboratory and immune testing to build a picture of each patient's infection status, immune function and systemic involvement. It runs in seven steps.

1

Full Medical History

Detailed review of symptom onset, progression, tick exposure history, prior testing results, previous treatments, and response to antibiotics. We assess the full timeline and pattern of illness to identify characteristic Lyme disease features.

2

Physical and Neurological Examination

Thorough physical examination with specific attention to neurological function, joint involvement, cardiac assessment, and signs of autonomic dysfunction. We evaluate for clinical markers of active infection and systemic inflammation.

3

Borrelia testing beyond the two-tier test

We use several methods beyond standard ELISA and Western blot: a Borrelia ELISpot (cellular immune response), a Western blot with expanded band analysis and, when indicated, direct detection methods. The ELISpot measures the T-cell response to Borrelia, which can be present when antibody levels are low.

4

CD57 natural killer cell analysis

Low CD57 counts were described in chronic Lyme disease (Stricker and Winger, 2001), but a later controlled comparison found no difference between patients with post-Lyme disease syndrome and controls (Marques et al., 2009). The evidence for CD57 as a marker is therefore limited. We measure it as one value among several and repeat it at follow-up, never as proof of infection or of response.

5

Co-infection panel

Testing for the common tick-borne co-infections: Bartonella, Babesia, Ehrlichia, Anaplasma, Rickettsia, Chlamydia pneumoniae, Mycoplasma pneumoniae and Yersinia. Each confirmed co-infection changes the treatment plan, because Babesia, for example, is a parasite and does not respond to the antibiotics used for Borrelia. The co-infections we test for

6

Immune Function Assessment

Evaluation of immune system markers including lymphocyte subsets, cytokine profiles, complement levels, and immunoglobulin levels to assess the degree of immune dysregulation and guide immunomodulatory treatment decisions.

7

Systemic Assessment

Additional testing as clinically indicated, including inflammatory markers (CRP, ESR, cytokines), thyroid function, adrenal function, hormonal panels, micronutrient levels, liver and kidney function, and heavy metal screening to evaluate the full systemic impact of chronic infection.

Close-up of hands holding an open navy folder with a few pages of unreadable printed results at a light oak desk
How we think about it

Clinical judgment guides our diagnosis

Lyme disease remains a clinical diagnosis supported by laboratory testing, not a laboratory diagnosis alone. No single test can definitively confirm or rule out chronic Borrelia infection. Our physicians integrate the full clinical picture, patient history, symptom pattern, physical examination findings, and results from multiple laboratory tests, to arrive at a diagnosis and treatment plan.

If you have been told that your tests are negative but your symptoms persist, write a short inquiry to the International Office, free of charge; it asks for your findings afterwards. A physician reads them before the video consultation and tells you which tests are still needed. The results of the work-up decide which modules of the Lyme treatment protocol apply to you; for patients from abroad, the page on the chronic Lyme program for international patients describes how records review, video consultation and admission run.

Testing methods compared

Standard testing and the hospital work-up

Standard testing

Commonly used in conventional medical settings:

  • ELISA screening (antibody-based)
  • Standard Western blot (limited bands)
  • Accuracy differs by stage of disease
  • Does not detect the cellular immune response
  • No co-infection screening included
  • No immune function assessment

The hospital work-up

Used at St. George Hospital:

  • Borrelia ELISpot (T-cell immune response)
  • Expanded Western Blot analysis
  • CD57 NK cell quantification
  • Full co-infection panel (8+ pathogens)
  • Immune system profiling
  • Inflammatory and metabolic markers
  • Clinical correlation with experienced physicians
Evidence

Evidence and limits

The evidence is graded, and the grade differs by test. That the accuracy of two-tier serology depends on the stage of disease is strong and comes from a systematic review and meta-analysis (Waddell et al., 2016). That ticks transmit several pathogens at once, so that a Borrelia-only work-up is incomplete, is strong (Sanchez-Vicente et al., 2019). The evidence for the ELISpot as a stand-alone diagnostic test is emerging, and the evidence for CD57 as a marker is limited (Stricker and Winger, 2001; Marques et al., 2009). This is why no single result decides the diagnosis here, and why the same markers are measured again at follow-up: a value that moves with treatment tells us more than a value read once.

What patients can expect

A typical diagnostic evaluation at St. George Hospital includes:

  • 90-minute initial physician consultation
  • Blood panel of 10+ tests from the hospital laboratory
  • Physical and neurological examination
  • Results reviewed within 5 to 10 working days
  • Treatment plan written from the findings
  • Full written report for your records
Frequently asked questions

Questions about Lyme diagnosis

Why was my Lyme test negative although I have symptoms?

The two-tier test detects antibodies, and its accuracy differs by stage of disease. Antibody levels can be low early in infection, after early antibiotics, or when the immune response is suppressed. A negative result in a long illness does not exclude Borrelia; it is one finding to be read with the history, the examination and the other tests.

Which tests do you use to diagnose chronic Lyme disease?

A Borrelia ELISpot for the cellular immune response, a Western blot with expanded band analysis, a CD57 natural killer cell count, a panel for the common tick-borne co-infections, and markers of immune function and inflammation, all in the hospital laboratory. The physician reads them together with your history and examination.

Is the CD57 test proof of Lyme disease?

No. Low CD57 counts were described in chronic Lyme disease, but a controlled comparison found no difference between patients with post-Lyme disease syndrome and controls. We record CD57 as one value among several and never as proof of infection or of response.

How long does the diagnostic work-up take?

The initial physician consultation lasts about 90 minutes. Blood is taken on the first day, and results are reviewed within 5 to 10 working days; the treatment plan is written from them. You receive a full written report for your records and your home physician.

Can I send results from my own country first?

Yes, and we ask you to. A physician reads your existing results, including negative ones, before the video consultation and tells you which tests are still needed. This avoids repeating what has already been done.

Related therapies

Treatments informed by our diagnostics

  • TherapyH.E.L.P. apheresis

    When diagnostics reveal elevated inflammatory markers and microclots, apheresis directly filters these from the bloodstream.

  • TherapyWhole-Body hyperthermia

    Diagnostic identification of persistent Borrelia and co-infections guides hyperthermia protocols targeting heat-sensitive organisms.

  • TherapyOzone therapy

    Immune panel results inform ozone therapy protocols that enhance immune function and provide antimicrobial support.

  • TherapyImmune therapy

    NK cell activity and lymphocyte subset results guide targeted immune restoration therapy for Lyme patients.

References

  1. The Accuracy of Diagnostic Tests for Lyme Disease in Humans, A Systematic Review and Meta-Analysis of North American Research.. PLoS One 2016. PMID 28002488
  2. Clinical Practice Guidelines by the IDSA, AAN and ACR: 2020 Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease.. Clin Infect Dis 2021. PMID 33483734
  3. Decreased CD57 lymphocyte subset in patients with chronic Lyme disease.. Immunol Lett 2001. PMID 11222912
  4. Natural killer cell counts are not different between patients with post-Lyme disease syndrome and controls.. Clin Vaccine Immunol 2009. PMID 19515868
  5. Polymicrobial Nature of Tick-Borne Diseases.. mBio 2019. PMID 31506314

Send a free inquiry

The initial inquiry is free of charge. The International Office reviews your message and your case directly and gets back to you.

Hours
Mon–Thu 08:00–17:00, Fri 08:00–14:00 German time (CET/CEST); in the US Mon–Thu 2–11 a.m. ET, Fri 2–8 a.m. ET.

Munich Airport (MUC), about 60 minutes by car.

CallSend a free inquiry